September 19, 2026
Upadoz / Upadacitinib and Psoriatic Arthritis: Targeting Inflammation at Its Source
ABSTRACT
Psoriatic arthritis (PsA) is a chronic inflammatory condition characterized by persistent joint inflammation, pain, stiffness, and progressive structural damage, often occurring alongside psoriasis. Upadacitinib (Upadoz) represents a targeted therapeutic approach that acts primarily through inhibition of Janus kinase 1 (JAK1), a key intracellular pathway involved in cytokine-mediated inflammatory signaling. By interfering with JAK–STAT signaling, upadacitinib can reduce downstream inflammatory activity and help control multiple manifestations of PsA. Clinical studies, including the SELECT-PsA trials, have demonstrated improvements in joint symptoms, physical function, and other disease manifestations among appropriately selected patients. Its oral once-daily administration also provides a convenient treatment option.
Statistics for Psoriatic Arthritis
- Psoriatic arthritis affects around 0.1%–0.2% of the worldwide population.
- Estimates place the prevalence at approximately 112–130 cases per 100,000 adults.
- Around 3–41 new cases per 100,000 person-years are reported globally.
- Rates tend to be higher in Europe and North America than in Asia and South America.
- Nearly 1 in 5 people with psoriasis may eventually develop psoriatic arthritis.
- Studies report considerable variation, with approximately 6%–41% of psoriasis patients developing joint disease.
- In about 68% of cases, psoriasis develops before arthritis symptoms.
- Approximately 15% experience skin and joint manifestations around the same time.
- About 17% develop joint symptoms before noticeable skin lesions.
Interesting Facts about Psoriatic Arthritis
- Skin and joints are connected: Psoriatic arthritis can affect both the skin and musculoskeletal system, although joint disease may sometimes occur without obvious psoriasis.
- Different people show different patterns: Psoriatic arthritis does not follow one fixed pattern, which can make diagnosis challenging.
- It is not simply “wear and tear”: Unlike osteoarthritis, PsA is an immune-mediated inflammatory arthritis.
- Arthritis can precede psoriasis: In a minority of patients, joint inflammation appears before any visible skin lesions, sometimes making the diagnosis difficult.
- The jaw can be affected: PsA may involve the temporomandibular joint (TMJ), potentially causing jaw pain, stiffness, or difficulty opening the mouth.
- Hidden inflammation may exist despite limited skin disease: The severity of psoriasis on the skin does not necessarily reflect the extent of underlying musculoskeletal involvement.
- It can mimic several other conditions: Depending on the joints and tissues involved, PsA may resemble rheumatoid arthritis, gout, osteoarthritis, or other spondyloarthropathies, making clinical pattern recognition important.
Introduction
Psoriatic arthritis (PsA) is a heterogeneous, chronic inflammatory musculoskeletal disease associated with psoriasis and characterized by involvement of peripheral joints, entheses, digits, and axial structures. The underlying immunopathology involves a complex network of cytokines and intracellular signaling pathways that sustain synovial inflammation, enthesitis, osteoproliferation, and bone erosion. Persistent inflammatory activity may consequently result in functional impairment, structural joint damage, and deterioration in quality of life. The clinical heterogeneity of PsA also presents challenges in achieving comprehensive disease control, particularly when multiple domains of disease activity coexist. Advances in understanding the molecular mechanisms underlying PsA have facilitated the development of targeted synthetic disease-modifying antirheumatic drugs (tsDMARDs). Among these, upadacitinib (Upadoz) is an orally administered, selective Janus kinase 1 (JAK1) inhibitor designed to interfere with intracellular cytokine signaling. JAK1 participates in signal transduction mediated by several cytokines implicated in PsA pathogenesis, including pathways associated with interleukin and interferon activity. Pharmacological inhibition of JAK1 therefore provides a mechanism for attenuating multiple inflammatory signals simultaneously.
Causes and Risk Factors of Psoriatic Arthritis
Psoriatic arthritis does not have a single identifiable cause. It is believed to develop through an interaction between genetic susceptibility, immune dysregulation, and environmental or mechanical triggers.
Genetic predisposition
A family history of psoriasis or PsA increases susceptibility. Several genetic variants, particularly within immune-regulatory genes, have been associated with disease development.
Immune-system dysregulation
Abnormal activation of immune pathways promotes the release of inflammatory mediators, including TNF-α, IL-17, and IL-23, contributing to joint and entheseal inflammation.
Psoriasis
The presence of cutaneous or nail psoriasis is the strongest established clinical risk factor for developing PsA, although arthritis can occasionally precede skin manifestations.
Environmental triggers
Infections, physical trauma, psychological stress, and other environmental influences may contribute to disease onset or flare in genetically predisposed individuals.
Joint or tissue injury
Mechanical stress or previous trauma may initiate inflammation at susceptible sites, particularly around entheses.
Obesity and metabolic factors
Excess adiposity is associated with an increased likelihood of PsA and may also contribute to greater inflammatory activity.
Smoking and lifestyle factors
Tobacco exposure and certain lifestyle-related factors have been investigated as potential modifiers of PsA risk and disease severity.
Gut–immune interactions
Alterations in the intestinal microbiome and mucosal immune responses are being investigated for their possible contribution to PsA development.
Signs and Symptoms of Psoriatic Arthritis
Psoriatic arthritis can present differently from one person to another. The pattern and intensity of symptoms may also change over time. The symptoms include:
Joint pain and tenderness
Affected joints may become painful, particularly during movement or prolonged activity. Tenderness can occur around the joint as well as in the surrounding tissues.
Joint swelling
Inflammation may cause visible swelling and a feeling of fullness around affected joints. Swelling can involve one or several joints.
Morning stiffness
Stiffness after waking or following prolonged inactivity is common. It may persist for some time and often improves as the joints become mobile.
Reduced range of motion
Inflammation, pain, and swelling can restrict normal joint movement, affecting activities such as walking, gripping, climbing stairs, or bending.
Dactylitis
An entire finger or toe may become diffusely swollen because inflammation involves multiple structures within the digit. This characteristic presentation is often described as a “sausage digit.
Enthesitis
Inflammation can occur where tendons or ligaments attach to bone. Common sites include the heel, achilles tendon, sole of the foot, and elbow, producing localized pain and tenderness.
Lower back or spinal symptoms
Some individuals develop inflammatory back pain involving the spine or sacroiliac joints. Stiffness may be more noticeable after rest and may improve with physical activity. .
Psoriatic skin lesions
Red, scaly, well-defined plaques may occur, commonly affecting the scalp, elbows, knees, or other areas.
Knee, ankle, or other large-joint involvement
PsA may affect larger peripheral joints, producing swelling, pain, stiffness, and functional limitations.
Asymmetrical joint involvement
Unlike some other inflammatory arthritides, PsA may affect different joints on opposite sides of the body, although symmetrical patterns can also occur.
Episodes of worsening
Symptoms may fluctuate, with periods of increased inflammation or flares followed by periods when symptoms become less pronounced.
Progressive functional impairment
Persistent untreated inflammation can eventually interfere with mobility, hand function, work, exercise, and other everyday activities.
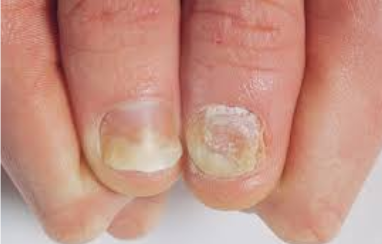
Nail abnormalities
Psoriatic arthritis may be accompanied by nail pitting, ridging, discoloration, thickening, crumbling, or separation of the nail from its underlying bed.
How Upadoz Works for the Management of Psoriatic Arthritis
Upadoz (upadacitinib) is a targeted oral therapy belonging to the Janus kinase (JAK) inhibitor class. Its principal pharmacological action is directed toward JAK1, an intracellular kinase involved in transmitting signals generated by several cytokines implicated in immune-mediated inflammation. Rather than neutralizing a cytokine outside the cell, upadacitinib interferes with the intracellular signaling machinery responsible for translating cytokine–receptor interactions into cellular responses.
Inhibition of JAK–STAT signaling
Following cytokine binding to its cellular receptor, JAK proteins become activated and phosphorylate signal transducers and activators of transcription (STATs). Activated STATs subsequently influence gene transcription within the nucleus, promoting immune-cell activation and inflammatory responses. Upadacitinib inhibits JAK activity and thereby reduces STAT phosphorylation and downstream transcriptional signaling.
Preferential JAK1 activity
Upadacitinib demonstrates greater inhibitory potency toward JAK1 than JAK2, JAK3, and TYK2. This pharmacological selectivity is relevant because JAK1 participates in signaling pathways associated with several inflammatory cytokines. However, JAK selectivity should not be interpreted as complete exclusivity; cytokine receptors frequently utilize JAK combinations, allowing JAK1 inhibition to influence multiple signaling pathways.
Suppression of inflammatory signaling
Psoriatic arthritis involves dysregulated immune signaling that contributes to synovitis, enthesitis, dactylitis, and other inflammatory manifestations. By attenuating JAK-dependent cytokine signaling, upadacitinib can reduce the intracellular inflammatory response and consequently decrease disease activity.
Impact across multiple disease domains
The therapeutic significance of JAK1 inhibition extends beyond reduction of joint inflammation. Clinical studies of upadacitinib in PsA have demonstrated improvements in peripheral arthritis, physical function, enthesitis, dactylitis, and psoriasis-related manifestations, supporting its role as a treatment capable of addressing several domains of this heterogeneous disease.
Thus, Upadoz acts at an important intracellular signaling checkpoint, interrupting cytokine-driven communication before it culminates in sustained inflammatory activity. This targeted mechanism provides the pharmacological basis for its use in appropriately selected patients with active PsA.
Who May Benefit from Upadacitinib?
Upadacitinib may be considered for patients with active psoriatic arthritis (PsA) when conventional treatment does not provide adequate disease control or cannot be tolerated. Patient selection should be individualized according to disease severity, affected domains, previous therapies, comorbidities, and safety considerations.
Patients with active PsA despite DMARD therapy
Individuals who continue to experience clinically significant joint inflammation, pain, stiffness, or functional impairment despite disease-modifying antirheumatic drugs may be candidates for targeted therapy.
Patients with inadequate response to biologic therapy
Clinical evidence supports upadacitinib in patients whose PsA remains active despite treatment with one or more biologic DMARDs. SELECT-PsA 2 specifically evaluated this treatment setting and demonstrated significantly greater clinical responses than placebo.
Patients with inadequate response or intolerance to TNF inhibitors
Current U.S. prescribing information identifies active PsA with inadequate response or intolerance to one or more TNF blockers as an indication for upadacitinib.
Patients with multiple disease manifestations
Upadacitinib may be particularly relevant when PsA involves several domains simultaneously, such as peripheral arthritis, enthesitis, dactylitis, axial symptoms, and psoriasis. Clinical trials have demonstrated improvements across several of these manifestations.
Patients requiring an oral targeted treatment
Upadacitinib is administered orally once daily, providing an alternative to injectable biologic therapies for appropriately selected patients.
Patients requiring substantial disease contro
Trial data have shown improvements in joint responses, physical function, psoriasis outcomes, and achievement of minimal disease activity, supporting its role in patients with clinically meaningful disease burden.
Importantly, upadacitinib is not appropriate for every patient with PsA. Before initiation, clinicians should evaluate infection risk, tuberculosis and viral hepatitis status where appropriate, blood counts, liver function, cardiovascular and thromboembolic risk, malignancy risk, pregnancy considerations, and potential drug interactions. The drug should also not be combined with other JAK inhibitors or biologic DMARDs. Therefore, the potential benefit of upadacitinib is greatest when its targeted mechanism, clinical profile, and safety considerations align with the individual patient’s disease characteristics and previous treatment history.
Ayurveda Insights
From an Ayurvedic perspective, psoriatic arthritis may be understood through the interplay of Vata and Pitta doshas with impaired Agni and accumulation of Ama, particularly when inflammatory manifestations involve the joints, skin, and soft tissues. The clinical picture may be considered in relation to Amavata when prominent features include pain, stiffness, swelling, and systemic inflammatory activity, while associated skin manifestations may reflect disturbances involving Rakta and Twak dhatus. Ayurvedic management focuses on identifying causative dietary and lifestyle factors, supporting Agni, reducing Ama, restoring doshic balance, and maintaining healthy tissue metabolism.
Pathogenesis of Psoriatic Arthritis
Ayurvedic interpretation of psoriatic arthritis can be developed through the concept of Samprapti, emphasizing the progression of pathological changes from the initial doshic disturbance to localization in specific tissues. Persistent exposure to causative factors may initiate Dosha Prakopa, followed by alteration of normal tissue nourishment and circulation. The disturbed Doshas subsequently gain access to susceptible Kha-Vaigunya (vulnerable sites), particularly the joints, tendons, and skin. Vata facilitates the movement and localization of the aggravated Doshas, while Pitta may intensify inflammatory and erythematous manifestations. In the musculoskeletal system, involvement of Sandhi, Asthi, and Majja, together with impaired function of Snayu, can account for pain, stiffness, swelling, and restricted movement. Concurrent involvement of Rakta and Twak provides an Ayurvedic framework for associated cutaneous manifestations.
Ayurvedic Alternatives for Upadoz/Upadacitinib by Planet Ayurveda
Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Psoriatic Arthritis according to Ayurvedic principles. The herbal formulations are:
- Boswellia Curcumin
- Coral Calcium Complex
- Bone Support
- Yograj Guggul
Upadoz/Upadacitinib Support Pack


Product description
1. Boswellia Curcumin
It contains two key ingredients, Shallaki (Boswellia serrata) and Curcumin (Curcuma longa), traditionally recognized for their anti-inflammatory properties. Boswellic acids have been investigated for their ability to modulate leukotriene synthesis through 5-lipoxygenase pathways, while curcumin may influence several inflammatory signaling mechanisms, including cytokine activity. Experimental research has also demonstrated effects of curcumin on inflammatory mediators relevant to psoriatic disease, including IL-17 and IFN-γ. Together, these ingredients may provide supportive management of joint discomfort, stiffness, and inflammatory symptoms associated with PsA.
Dosage: 1 capsule twice a day with plain water after meals.
2. Coral Calcium Complex
It is an Ayurvedic mineral formulation containing Parval Pishti (coral), Akik Pishti (agate), Jawar Mohra Pishti, Kamdudha Ras, Mukta Pishti (pearl), and Guduchi Satva (Tinospora cordifolia). Its calcium-containing ingredients may provide nutritional support for bone strength and mineral balance, which can be relevant when chronic inflammatory joint disease affects musculoskeletal health. Guduchi is traditionally described for its anti-inflammatory and Rasayana properties.
Dosage: 1 capsule twice a day with plain water after meals.
3. Bone Support
It is an Ayurvedic formulation containing Shuddha Laksha (Laccifer lacca), Suhanjana Beej (Moringa oleifera), Hadjod (Cissus quadrangularis), Arjun (Terminalia arjuna), Praval Pishti (Corallium rubrum), and Mukta (pearl calcium). Its ingredients are traditionally used to support bone nourishment, mineral balance, and musculoskeletal strength. Hadjod has been investigated for its potential effects on bone-related parameters.
Dosage: 1 capsule twice a day with plain water after meals.
4. Yograj Guggul
It is a classical Ayurvedic polyherbal formulation containing Commiphora mukul (Guggulu), Plumbago zeylanica (Chitraka), Emblica officinalis (Amalaki), Cyperus rotundus (Musta), Terminalia bellirica (Bibhitaki), Piper longum (Pippali), Carum copticum, Tribulus terrestris, and several other botanicals. In Ayurvedic practice, its combination is traditionally used in disorders involving joint stiffness, pain, and impaired musculoskeletal function. The formulation may therefore provide supportive care for musculoskeletal symptoms associated with PsA, particularly discomfort and restricted mobility.
Dosage: 1 tablet twice a day with lukewarm water.
Conclusion
Upadacitinib has emerged as an important targeted option for achieving broader disease control in patients with active psoriatic arthritis. Its selective JAK1-directed activity provides a pharmacological means of interrupting several cytokine-dependent inflammatory pathways. Its oral administration may also offer practical advantages for appropriately selected patients. Overall, upadacitinib represents a significant advancement in targeted PsA management, particularly when sustained suppression of multidimensional inflammatory activity remains difficult to achieve.

Dr. Vikram Chauhan
https://www.planetayurveda.comDr. Vikram Chauhan (MD - Ayurveda) is a Globally Renowned Ayurveda Physician with Expertise of more than 25 Years. He is the CEO & Founder of http://www.PlanetAyurveda.com, a leading Ayurveda Brand, Manufacturing, and Export Company with a Chain of Clinics and Branches in the US, Europe, Africa, Southeast Asia, India, and other parts of the World. He is also an Ayurveda Author who has written Books on Ayurveda, translated into Many European Languages. One of his Books is "Ayurveda – God’s Manual for Healing". He is on a Mission to Spread Ayurveda All Over the Planet through all the Possible Mediums. With his Vast Experience in Herbs and their Applied Uses, he is successfully treating Numerous Patients suffering from Various Ailments with the help of the Purest Herbal Supplements, Diet, and Lifestyle, according to the Principles of Ayurveda. For More Details, visit - www.planetayurveda.com, www.alwaysayurveda.com
View more posts from this author

