Category: Child Health

Herbal Remedies of Seasonal Affective Disorder (SAD) – Causes, Symptoms, Diagnosis & Treatment

ABSTRACT

Seasonal Affective Disorder (SAD) is a form of recurrent mood disturbance in which depressive symptoms appear during a particular season and improve when the season changes. It is commonly associated with reduced exposure to natural daylight, especially during autumn and winter, and may present with persistent sadness, low motivation, fatigue, increased sleep, changes in appetite, difficulty concentrating, and social withdrawal. Alterations in the body’s circadian rhythm, melatonin secretion, serotonin activity, and sleep-wake cycle may contribute to its development. Although SAD is often considered a subtype of major depressive disorder, its predictable seasonal pattern distinguishes it from many other depressive conditions. Diagnosis requires careful assessment of the timing, duration, severity, and recurrence of symptoms while excluding other medical or psychiatric causes.

Seasonal Affective Disorder (SAD)

STATISTICS FOR SEASONAL AFFECTIVE DISORDER

  • SAD affects approximately 1%–10% of the general population.
  • Pooled prevalence is about 5.01%, while subsyndromal SAD is around 9.37%.
  • Summer-pattern SAD accounts for approximately 0.57%.
  • SAD may represent around 10% of diagnosed depressive episodes.
  • Symptoms generally persist for 4–5 months each year.
  • SAD most commonly begins during young adulthood, particularly between 18 and 30 years.

INTERESTING FACTS ABOUT SEASONAL AFFECTIVE DISORDER

  • It can follow a calendar: SAD often returns around the same time each year, making its pattern surprisingly predictable.
  • Location matters: SAD tends to be more common in regions with greater seasonal changes in daylight.
  • Summer SAD exists: SAD is not limited to winter; a smaller group of people experience a seasonal pattern during summer.
  • It can occur in children: Although commonly recognized in adults, seasonal mood changes can also affect children and adolescents.
  • It is more than the “winter blues”: SAD is a clinically recognized condition, whereas ordinary wintertime low mood may not meet diagnostic criteria.
  • Daylight can influence biological timing: Seasonal changes in daylight can interact with the body’s internal clock, which helps explain why SAD follows a seasonal rhythm.
  • The pattern can change: A person’s seasonal mood pattern may vary over different stages of life rather than remaining identical every year.
  • Geography does not tell the whole story: Latitude, climate, lifestyle, individual susceptibility, and access to daylight can all contribute to differences in how frequently SAD is reported.

INTRODUCTION

Seasonal Affective Disorder (SAD) is a clinically recognized mood disorder characterized by a recurring relationship between depressive episodes and a particular time of the year. Unlike depressive conditions that may occur without a recognizable seasonal pattern, SAD follows a temporal rhythm, with periods of emotional disturbance occurring during specific months and remission during other parts of the year. This recurring nature makes seasonality an important component of clinical assessment. SAD is most commonly associated with the autumn and winter months, although a smaller proportion of individuals experience symptoms during spring or summer. Its occurrence varies across geographical regions, and differences in daylight exposure across seasons have contributed to considerable interest in the relationship between environmental changes and mental health. The condition may influence daily functioning, interpersonal relationships, academic or professional performance, and overall quality of life.

CAUSES AND RISK FACTORS OF SEASONAL AFFECTIVE DISORDER

This disorder develops through a combination of biological, environmental, genetic, and lifestyle-related factors. The causes and risk factors are as follows in detail:

Seasonal changes in daylight

Reduced daylight during certain seasons may affect brain systems involved in mood regulation and biological timing.

Circadian rhythm disruption

Changes in the light-dark cycle can disturb the body’s internal biological clock and alter normal sleep-wake regulation.

Altered serotonin activity

Seasonal changes may influence serotonin pathways involved in emotional regulation, potentially contributing to depressive symptoms in susceptible individuals.

Melatonin changes

Variations in light exposure can affect melatonin production and timing, influencing sleep patterns and circadian regulation.

Genetic susceptibility

A family history of depression, bipolar disorder, or SAD may increase an individual’s vulnerability.

Female sex

SAD has been reported more frequently among women than men, although the reasons for this difference remain incompletely understood.

Higher latitude

Living farther from the equator, where seasonal differences in daylight are greater, is associated with higher reported rates of winter-pattern SAD.

Bipolar disorder

People with bipolar disorder may experience a seasonal pattern in the timing of depressive or manic/hypomanic episodes.

Environmental and lifestyle factors

Seasonal changes in daily routine, physical activity, social interaction, and outdoor exposure may contribute to vulnerability in susceptible individuals.

SIGNS AND SYMPTOMS OF SEASONAL AFFECTIVE DISORDER

The clinical presentation of SAD can extend beyond ordinary low mood. Its recurring seasonal pattern and distinctive changes in biological and behavioral functioning are particularly important when recognizing the disorder. The signs and symptoms include:

Atypical depressive features

Winter-pattern SAD may show increased sleep, increased appetite, carbohydrate cravings, and weight gain rather than the reduced sleep and appetite often associated with typical depression.

Seasonal hypersomnia

A person may sleep substantially longer than usual yet continue to feel unrefreshed or excessively sleepy during the day.

Season-linked energy shift

A noticeable reduction in physical and mental drive may develop during the affected season, often interfering with normal daily activities.

Carbohydrate-focused cravings

Some individuals develop a strong preference for carbohydrate-rich foods, particularly during the colder or darker months.

Seasonal social withdrawal

Individuals may progressively reduce social interaction and participation in activities that they normally maintain.

Distinctive cognitive slowing

Thinking, concentration, decision-making, and mental responsiveness may feel noticeably slower during the affected season.

Seasonal hypersensitivity to environmental change

Mood and functioning may fluctuate noticeably as daylight duration and seasonal conditions change.

Functional impairment with repetition

The symptoms become clinically significant when they repeatedly interfere with occupational, academic, interpersonal, or everyday functioning across seasonal cycles.

Summer-pattern presentation

Although less common, summer SAD can present with a different pattern, including reduced sleep, decreased appetite, weight loss, agitation, and increased restlessness.

DIAGNOSIS OF SEASONAL AFFECTIVE DISORDER

The diagnosis of Seasonal Affective Disorder (SAD) is primarily clinical and depends on identifying a consistent relationship between depressive episodes and a particular season. There are various diagnostic tests that are as follows:

Clinical History

The clinician records the onset, duration, severity, and recurrence of depressive symptoms. Changes in mood, sleep, appetite, energy, concentration, and daily functioning are assessed.

Assessment of Winter or Summer Pattern

Winter pattern may identify hypersomnia, increased appetite, carbohydrate cravings, and seasonal weight gain.  Summer patterns may reveal insomnia, reduced appetite, weight loss, agitation, or increased restlessness.

Symptom Questionnaires

Standardized depression or SAD-related questionnaires may be used to measure symptom severity and support the clinical assessment. Questionnaires are supportive tools rather than substitutes for professional diagnosis.

Functional Assessment

The clinician evaluates whether seasonal symptoms interfere with work, education, relationships, self-care, or everyday responsibilities. This helps distinguish clinically significant SAD from temporary seasonal changes in mood.

Psychiatric Evaluation

Current or previous episodes of major depression and bipolar disorder should be explored because SAD can occur in association with these conditions.

MANAGEMENT OF SEASONAL AFFECTIVE DISORDER

It should be individualized according to the seasonal pattern, severity of depression, functional impairment, previous episodes, and coexisting psychiatric or medical conditions. The management may require various approaches like:

Bright Light Therapy

It is a major treatment for winter-pattern SAD. A light box providing approximately 10,000 lux is commonly used. It is generally used in the morning, often for about 20–45 minutes daily, according to clinical guidance and the device’s instructions. The device should be designed specifically for SAD and should filter out potentially harmful ultraviolet (UV) radiation.

Cognitive Behavioral Therapy

It can help modify negative seasonal thoughts and unhelpful behavioral patterns. CBT for SAD may incorporate behavioral activation, encouraging regular engagement in meaningful activities. It can also help improve coping skills, stress management, sleep habits, and adherence to healthy routines.

Antidepressant Medications

These may be considered when symptoms are moderate to severe, persistent, or inadequately controlled with non-drug approaches. Bupropion extended-release has been used for prevention of recurrent seasonal depressive episodes. Selective serotonin reuptake inhibitors (SSRIs) and other antidepressants may also be considered depending on the clinical presentation.

Vitamin D Assessment

Vitamin D supplementation may be considered particularly in winter-pattern SAD when deficiency is present. Spending time outdoors during daylight hours can increase exposure to natural light. Morning outdoor activity may be incorporated into the daily routine, particularly during seasons with reduced daylight.

Structured Sleep Routine

Maintaining consistent sleep and wake times can help support regular circadian rhythms. Excessive daytime sleeping and prolonged naps should generally be avoided when they worsen the sleep-wake pattern.

Management of Summer-Pattern SAD

It generally focuses on evidence-based treatments for depression, including psychotherapy and appropriate medication when indicated.

Social and Behavioral Support

Maintaining regular contact with family, friends, colleagues, and supportive social networks can help counter seasonal withdrawal. Relaxation practices such as meditation, yoga, and stress-management techniques may complement the primary treatment plan.

AYURVEDA INSIGHTS

From an Ayurvedic perspective, Seasonal Affective Disorder can be understood through the interaction of Manas (mind), Dosha, Agni (metabolic and digestive function), and seasonal changes (Ritucharya). The transition between seasons may influence Vata and Kapha, particularly when changes in coldness, dryness, reduced sunlight, inactivity, and daily routine disturb the body’s physiological balance. Kapha aggravation may be associated with heaviness, lethargy, excessive sleep, and reduced motivation, while Vata imbalance may contribute to mental restlessness, irregular sleep, and emotional instability. Ayurveda also emphasizes the role of Sattva (mental clarity and balance) and considers regular sleep, appropriate diet, physical activity, exposure to natural daylight, meditation, yoga, Abhyanga (oil massage), and adherence to seasonal routines as supportive measures for maintaining mental and physiological equilibrium. Individual assessment of Prakriti (constitution), Vikriti (current imbalance), Agni, and lifestyle can help guide a personalized Ayurvedic approach.

PATHOGENESIS OF SEASONAL AFFECTIVE DISORDER

From an Ayurvedic viewpoint, the development of seasonal mood disturbance may be conceptualized as a Samprapti (disease process) arising from an incompatibility between the individual’s internal state and recurring seasonal influences. Kala (time) and Ritu (season) can modify Dosha activity and bodily functions, while disruption of Ritucharya (seasonal regimen) may interfere with the body’s natural adaptation. In susceptible individuals, this may initiate Dosha Vaishamya (functional imbalance), followed by disturbance in the normal functions of Manas (mind). Predominance of Tamas may manifest as mental inertia and reduced engagement, whereas disturbed Rajas may interfere with emotional steadiness and mental organization. Continued imbalance can affect Manovaha Srotas, producing dysfunction in the pathways responsible for mental activity and emotional regulation. If these changes persist, Dhi (intellectual discrimination), Dhriti (mental restraint), and Smriti (memory) may become functionally impaired, influencing motivation, decision-making, and adaptation to routine activities.

HERBAL REMEDIES FOR SEASONAL AFFECTIVE DISORDER BY PLANET AYURVEDA

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Seasonal Affective Disorder according to Ayurvedic principles. The herbal formulations are:

  1. Neurogenie Capsules
  2. Ashwagandha Capsules
  3. Calm Easy Tea

Herbal Remedies For Seasonal Affective Disorder (SAD)

Buy Now Herbal Remedies For Seasonal Affective Disorder (SAD)

Buy Now Herbal Remedies For Seasonal Affective Disorder (SAD)

PRODUCT DESCRIPTION

1. Neurogenie Capsules

These contain Brahmi (Bacopa monnieri) and Ashwagandha (Withania somnifera), two traditionally used Ayurvedic herbs associated with mental and nervous-system support. In the context of Seasonal Affective Disorder, this formulation may be considered as a supportive Ayurvedic approach for maintaining mental balance, coping with stress, and supporting healthy sleep and cognitive function during seasonal changes. Brahmi is traditionally valued as a Medhya Rasayana (cognitive rejuvenative), while Ashwagandha is regarded as a Rasayana with adaptogenic properties.

Dosage: 2 capsules twice a day after meals with plain water.

2. Ashwagandha Capsules

These contain Ashwagandha (Withania somnifera), an Ayurvedic Rasayana (rejuvenative herb) traditionally used to support resilience, mental balance, and overall wellbeing. In the context of Seasonal Affective Disorder, Ashwagandha may be considered as a supportive Ayurvedic option for individuals experiencing stress, disturbed sleep, low energy, or difficulty adapting to seasonal changes. Its traditional use is particularly associated with promoting calmness and supporting healthy nervous-system function.

Dosage: 1 capsule twice a day after meals with plain water.

3. Calm Easy Tea

It contains a combination of Ashwagandha (Withania somnifera), Brahmi (Bacopa monnieri), Licorice (Glycyrrhiza glabra), Green Tea (Camellia sinensis), Ginger (Zingiber officinale), and Cinnamon (Cinnamomum verum). In an Ayurvedic supportive approach to Seasonal Affective Disorder, this herbal tea may be incorporated into a wellness routine aimed at maintaining mental calmness, relaxation, and daily balance during seasonal changes. Ashwagandha and Brahmi are traditionally valued for supporting mental wellbeing, while ginger and cinnamon are traditionally used to support digestion. Green tea provides a mild source of caffeine and antioxidants.

Dosage: 1 cup daily.

DIETARY TIPS FOR SEASONAL AFFECTIVE DISORDER

The foods which can be included in the diet are as follows:

  • Green leafy vegetables: Kale, spinach and similar greens supply folate and other micronutrients that support overall brain health.
  • Whole grains: Oats, barley, and quinoa provide B-group vitamins that contribute to normal nervous-system function.
  • Dairy foods: Fresh milk, curd, and other dairy products can provide protein, calcium, and other nutrients as part of a balanced diet.
  • Nuts and seeds: Almonds, flaxseeds, and other nuts and seeds offer healthy fats, including plant-based omega-3 fatty acids, along with minerals that support neurological health.
  • Fruits: Avocados, berries, and other nutrient-dense fruits provide vitamins, minerals, fiber, and antioxidant compounds that contribute to overall wellbeing.

The foods to avoid in this disorder include:

  • Highly processed foods and added sugars: Frequent intake may cause rapid fluctuations in blood glucose and energy levels, which can affect overall mood and wellbeing.
  • Excessive caffeine and alcohol: High caffeine intake may interfere with sleep, while alcohol can disrupt normal sleep quality and emotional balance.
  • Excessively spicy foods: Very spicy meals may aggravate Pitta and, in susceptible individuals, contribute to digestive discomfort and imbalance of Vata.
  • Heavy and excessively fatty meats: These may feel difficult to digest and, from an Ayurvedic perspective, can aggravate Kapha, contributing to heaviness and sluggishness.
  • Stale or repeatedly reheated foods: Ayurveda recommends favoring freshly prepared meals, as stale foods may be considered less supportive of balanced digestion.

CONCLUSION

Early recognition, regular monitoring, and an individualized care plan are important for maintaining emotional wellbeing and preventing seasonal disturbances from affecting daily life. Consistent sleep, balanced nutrition, physical activity, adequate daylight exposure, meaningful social interaction, and appropriate psychological support can contribute to better overall functioning. Preventive strategies may also be considered when a recurring seasonal pattern is established. From an Ayurvedic perspective, following Ritucharya (seasonal regimen), supporting Agni (digestive and metabolic function), and promoting Sattva (mental clarity and stability) may offer complementary support for maintaining balance through seasonal transitions.
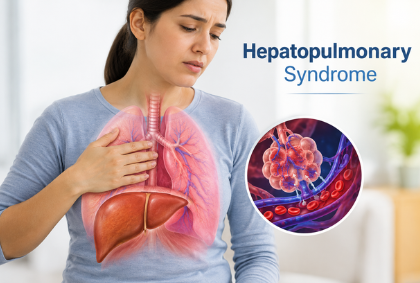

Herbal Remedies of Hepatopulmonary syndrome – Causes, Symptoms, Diagnosis & Treatment

Abstract

Hepatopulmonary syndrome is a significant pulmonary complication that develops in individuals with chronic liver disease and portal hypertension. The vascular changes interfere with efficient gas exchange and may lead to symptoms such as shortness of breath, fatigue, cyanosis, and worsening breathlessness in an upright position. The severity of hepatopulmonary syndrome can vary from mild oxygen deficiency to severe respiratory impairment, adversely affecting quality of life and overall prognosis. Its diagnosis generally involves the assessment of arterial oxygen levels and the detection of intrapulmonary vascular dilatation through appropriate imaging techniques. Early recognition is important because respiratory symptoms may be overlooked in patients with advanced liver disorders.

Hepatopulmonary syndrome

Statistics for Hepatopulmonary syndrome

  • Hepatopulmonary syndrome (HPS) is estimated to affect approximately 4% to 19% of patients with liver cirrhosis.
  • The occurrence of HPS increases in individuals undergoing evaluation for liver transplantation, with a reported prevalence of around 17.2%.
  • Studies have reported HPS in approximately 26.1% of patients with portal hypertension who are being assessed for liver transplantation.
  • A pooled prevalence of nearly 21.6% has been observed among patients undergoing or associated with liver transplantation.
  • Hospitalized patients with HPS may experience significant complications, with reported inpatient mortality rates ranging from 12.4% to 12.6%.

Interesting Facts about Hepatopulmonary syndrome

  • A liver disease can cause a lung oxygenation problem: Although the lungs may appear structurally normal, liver dysfunction can trigger abnormal widening of blood vessels inside the lungs, reducing efficient oxygen transfer.
  • Symptoms may worsen when standing: A distinctive feature of HPS is platypnea, in which shortness of breath becomes worse in an upright position and improves when lying down.
  • Oxygen levels can drop on sitting or standing: This phenomenon is called orthodeoxia and is considered an important clinical clue for HPS.
  • The liver and lungs are connected through circulating substances: In advanced liver disease, substances that are normally cleared or regulated by the liver may contribute to increased production of vasodilators, particularly nitric oxide, in the lungs.
  • A patient may have severe oxygen deficiency with relatively mild respiratory symptoms: Some individuals gradually adapt to low oxygen levels and may not recognize the seriousness of their condition.
  • A special “bubble test” can help detect it: Contrast echocardiography using agitated saline can demonstrate abnormal passage of microbubbles through dilated blood vessels in the lungs.
  • Clubbing and bluish discoloration may occur: Long-standing low oxygen levels can cause finger clubbing and cyanosis in some patients.

Introduction

Hepatopulmonary syndrome (HPS) is an important extrahepatic complication of chronic liver disease that affects the relationship between the liver, pulmonary circulation, and oxygen exchange. It is primarily associated with cirrhosis and portal hypertension, although it may also occur in other forms of chronic hepatic dysfunction. The condition develops when abnormal changes in the pulmonary blood vessels interfere with the normal transfer of oxygen from the lungs into the bloodstream. Dilatation of small pulmonary vessels increases the distance between inhaled oxygen and circulating red blood cells, resulting in impaired oxygenation. The underlying mechanisms of hepatopulmonary syndrome are complex and involve disturbances in vascular regulation. Increased production of vasodilatory substances, inflammatory mediators, and alterations in pulmonary vascular tone are considered important contributors. Nitric oxide is believed to play a major role in the excessive widening of blood vessels within the lungs. These changes may gradually lead to reduced oxygen levels and progressive respiratory discomfort. Hepatopulmonary syndrome can significantly affect daily functioning and overall health status, making it an important complication requiring greater clinical awareness in individuals with chronic liver disorders.

Causes of Hepatopulmonary syndrome

Hepatopulmonary syndrome develops mainly as a consequence of chronic liver dysfunction and portal hypertension, which produce abnormal changes in the blood vessels of the lungs. The central abnormality involves excessive widening of small pulmonary blood vessels. This dilatation interferes with the normal movement of oxygen from the air spaces of the lungs into the bloodstream, resulting in reduced arterial oxygen levels. Several liver-related conditions can contribute to the development of HPS.

  • Cirrhosis – It is the most common condition associated with hepatopulmonary syndrome.These changes can increase the levels of vasodilatory and inflammatory substances in the bloodstream. When these substances reach the lungs, they may promote abnormal widening of pulmonary blood vessels and contribute to impaired oxygen exchange.
  • Portal hypertension – Increased pressure within the portal venous system is another important factor linked with HPS. The syndrome may develop in individuals with portal hypertension even when cirrhosis is not fully established. Altered blood flow and the development of portosystemic shunting can allow various circulating substances to bypass normal hepatic processing, potentially affecting the pulmonary circulation and causing excessive vascular dilatation.
  • Other chronic liver disorders – Chronic hepatic disorders that produce portal hypertension or substantial impairment of liver function may create conditions favorable for the development of abnormal pulmonary vascular changes.
  • Acute liver failure – Although less common, severe acute liver dysfunction has also been associated with hepatopulmonary syndrome. Sudden and marked impairment of liver function can disrupt normal vascular regulation and alter the balance of circulating mediators involved in blood vessel tone.
  • Portal vein thrombosis – Obstruction of the portal vein by a blood clot can increase pressure within the portal circulation and produce significant alterations in hepatic blood flow. In some cases, these circulatory disturbances may contribute to the development of pulmonary vascular abnormalities characteristic of HPS.
  • Congenital hepatic fibrosis – It can lead to portal hypertension despite relatively preserved liver cell function. The resulting changes in portal circulation may occasionally be associated with the pulmonary vascular dilatation seen in hepatopulmonary syndrome.

Signs and Symptoms of Hepatopulmonary syndrome

Hepatopulmonary syndrome may not produce noticeable symptoms in many individuals, particularly during its early stages. When clinical manifestations appear, they may include:

  • Shortness of breath – Difficulty in breathing may become more prominent while sitting or standing and may improve after lying down. This characteristic positional breathlessness is known as platypnea.
  • Clubbing of fingers – Prolonged reduction in oxygen levels can cause the fingertips to become enlarged, rounded, and bulbous. The nails may also appear more curved than normal.
  • Spider angiomas – Small dilated blood vessels may become visible beneath the surface of the skin, often forming a pattern similar to the legs of a spider.
  • Cyanosis – Insufficient oxygen in the blood can cause changes in the natural color of the lips, tongue, skin, or nail beds. A bluish discoloration may be more apparent in lighter skin tones, whereas grayish or pale changes may be easier to notice on the lips or tongue in darker skin tones.
  • Orthodeoxia – Some individuals experience a reduction in blood oxygen levels when moving from a lying position to an upright position. This unusual feature may occur along with platypnea and is considered a characteristic manifestation of hepatopulmonary syndrome.
  • Fatigue and reduced exercise tolerance – Persistent low oxygen levels can contribute to tiredness, weakness, and difficulty performing physical activities that were previously well tolerated.

Diagnosis of Hepatopulmonary syndrome

The diagnosis of hepatopulmonary syndrome (HPS) is based on the presence of liver disease, impaired oxygenation, and abnormal dilatation of blood vessels within the lungs. The diagnosis include:

  • Medical history – HPS should be considered in individuals with chronic liver disease or portal hypertension who develop unexplained shortness of breath. Particular attention should be given to platypnea, in which breathing difficulty becomes more pronounced in the sitting or standing position and improves when the person lies down.
  • The diagnostic triad of HPS – Hepatopulmonary syndrome is generally characterized by three major components: Presence of chronic liver disease and/or portal hypertension, impaired oxygenation of arterial blood without another sufficient explanation, intrapulmonary vascular dilatation (IPVD), meaning abnormal widening of blood vessels within the lungs.
  • Pulse oximetry – Pulse oximetry is a simple and non-invasive method used to assess oxygen saturation. It can help identify reduced oxygen levels and may be useful as an initial screening tool in patients with liver disease who experience respiratory symptoms.
  • Arterial blood gas analysis (ABG) – It measures parameters such as the partial pressure of oxygen in arterial blood and can help determine the severity of hypoxemia. ABG testing is particularly important in patients with significant respiratory symptoms or suspected advanced HPS.
  • Contrast-enhanced echocardiography  – The timing of bubbles reaching the left chambers of the heart can help identify the location of abnormal blood flow. In intrapulmonary vascular dilatation, microbubbles generally appear in the left atrium after passing through several cardiac cycles. This delayed appearance helps distinguish an intrapulmonary shunt from an abnormal communication located directly within the heart.
  • Pulmonary angiography – It can demonstrate abnormal patterns in the pulmonary blood vessels, including diffuse, fine, or patchy vascular abnormalities associated with intrapulmonary vascular dilatation.
  • Technetium-99m macroaggregated albumin scan – A nuclear medicine scan using technetium-99m-labelled macroaggregated albumin may also be used to demonstrate abnormal passage of blood through dilated pulmonary vessels. In the presence of significant intrapulmonary shunting, some particles can bypass the lungs and reach organs such as the brain or kidneys.

Management of Hepatopulmonary syndrome

Management of hepatopulmonary syndrome (HPS) focuses on correcting hypoxemia, controlling the underlying liver disease, monitoring disease progression, and evaluating the patient for liver transplantation. The management strategies include:

Treatment of the underlying liver disease

Cirrhosis, portal hypertension, viral hepatitis, alcohol-related liver disease, metabolic liver disease, and other causes of chronic hepatic injury should be managed according to their specific clinical setting. Maintaining overall liver health is important because HPS is closely associated with hepatic dysfunction and abnormal portal circulation.

Supplemental oxygen

Oxygen supplementation is the principal supportive treatment for patients with clinically important hypoxemia. It increases the amount of oxygen available to the tissues and can reduce symptoms such as breathlessness, fatigue, and reduced exercise tolerance. Oxygen may be administered continuously or during periods of activity or sleep according to the degree of oxygen deficiency and individual requirements.

Liver transplantation and recovery

Following successful transplantation, the abnormal pulmonary vasodilatation and impaired oxygen exchange usually improve progressively rather than immediately. Oxygen levels can increase over time as the abnormal pulmonary circulation gradually returns toward normal.

Management of severe hypoxemia

Severe hypoxemia requires close monitoring and management in a specialized setting. Supplemental oxygen is used to maintain adequate oxygenation while definitive treatment is considered. Patients undergoing liver transplantation with severe HPS can occasionally develop profound hypoxemia immediately after transplantation and may require intensive respiratory support.

Embolization in selected patients

Pulmonary angiographic intervention may have a role in the uncommon patient who has a discrete, significant arteriovenous communication rather than predominantly diffuse pulmonary vascular dilatation. Coil or other embolization techniques can sometimes reduce abnormal shunting and improve oxygenation.

Pharmacological therapy

Several medications have been investigated for HPS, including methylene blue, pentoxifylline, garlic preparations, mycophenolate mofetil, somatostatin analogues, nitric-oxide pathway inhibitors, and anti-angiogenic drugs.

Nutritional and general support

Patients with advanced liver disease and HPS may be vulnerable to malnutrition, muscle wasting, fatigue, and reduced physical capacity. Adequate nutritional support, appropriate physical activity according to tolerance, avoidance of alcohol, vaccination where appropriate, and prevention or prompt treatment of infections are important components of overall care.

Ayurveda Insights

In classical Ayurvedic texts, its clinical features may be understood through the concepts of Yakrit (liver), Rakta (blood), Pranavaha Srotas (respiratory channels), Agni, and Dosha imbalance. Chronic liver dysfunction may be associated with impaired Agni and disturbed Pitta, while breathlessness and reduced functional capacity may indicate involvement of Vata and Pranavaha Srotas. Ayurvedic management may focus on supporting liver function, maintaining healthy digestion, reducing metabolic disturbances, and strengthening the body’s tissues through suitable Deepana-Pachana and Rasayana approaches. Treatment should be individualized according to Prakriti and disease status.

Pathogenesis of Hepatopulmonary syndrome

Chronic hepatic dysfunction may lead to Agni Dushti, causing impaired metabolism and disturbance of Pitta Dosha, which is closely associated with Yakrit (liver) and Rakta Dhatu. Persistent Dosha imbalance may contribute to Rakta and Rasavaha Srotas Dushti, while progressive involvement of Vata Dosha can affect Pranavaha Srotas. This may manifest as Shwasa (breathlessness), fatigue, and reduced functional capacity. Prolonged disease progression may also result in Bala and Ojas Kshaya, further compromising systemic strength. Thus, an Ayurvedic interpretation may be understood as a sequence of Agni Dushti, Dosha Prakopa, Dhatu and Srotas Dushti, followed by Pranavaha Srotas involvement.

Home Remedies of Hepatopulmonary syndrome by Planet Ayurveda

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Hepatopulmonary syndrome according to Ayurvedic principles. The herbal formulations are:

  1. Yakrit Plihantak Churna
  2. Phyllanthus Niruri
  3. Punarnava Mandur
  4. Praanrakshak Churna
  5. Boswellia Curcumin
  6. Vasaka Capsules

Herbal Remedies of Hepatopulmonary syndrome

Buy Now Herbal Remedies of Hepatopulmonary syndrome

Buy Now Herbal Remedies of Hepatopulmonary syndrome

Product description:

1. Yakrit Plihantak Churna

It contains a combination of Ayurvedic herbs traditionally used to support Yakrit (liver) function and Rakta metabolism. Its ingredients include Bhumi Amla, Bhringraj, Kalmegh, Kaasni, Katuki, Sharpunkha, Punarnava, and Makoy. In the context of hepatopulmonary syndrome, this formulation may be considered as supportive Ayurvedic care aimed at maintaining hepatic function and addressing factors associated with chronic liver dysfunction. Bhumi Amla, Bhringraj, Kalmegh, Kaasni, and Katuki are traditionally valued for their hepatoprotective and Pitta-balancing properties, while Sharpunkha is used in classical practice for liver and splenic support. Punarnava is traditionally associated with fluid balance and supports healthy renal function, whereas Makoy is recognized for its traditional use in hepatic and inflammatory conditions. Collectively, these herbs may support digestion, metabolism, and liver health

Dosage: 1 teaspoonful twice a day with plain water after meals.

2. Phyllanthus Niruri

It is traditionally regarded as a liver-supportive herb in Ayurveda and is used in formulations intended to maintain hepatic function. Bhumi Amla extract contains bioactive constituents such as lignans, flavonoids, tannins, and polyphenolic compounds, which have demonstrated antioxidant and hepatoprotective activities. In the context of hepatopulmonary syndrome, maintaining liver health may be relevant because HPS develops in association with chronic hepatic dysfunction and portal hypertension. Bhumi Amla extract may therefore be considered as a supportive measure for hepatic wellness, particularly when underlying liver dysfunction is being managed.

Dosage: 2 capsules twice a day with plain water after meals.

3. Punarnava Mandur

It is an Ayurvedic formulation traditionally used to support liver function, Rakta Dhatu, digestion, and fluid balance. In the context of hepatopulmonary syndrome, its traditional actions may provide supportive care by promoting healthy digestion and metabolism, supporting hepatic function, and maintaining Rakta and fluid balance. Punarnava is particularly valued for its traditional use in liver and fluid-related disorders, while Amalaki and Haridra provide antioxidant support.

Dosage: 2 tablets twice a day with lukewarm water.

4. Praanrakshak Churna

It is an Ayurvedic herbal formulation containing Shirish (Albizia lebbeck), Vaasa (Adhatoda vasica), Anantmool (Tylophora asthmatica), Dalchini (Cinnamomum zeylanicum), Bharangi (Clerodendrum serratum), Kantkari (Solanum xanthocarpum), and Mulethi (Glycyrrhiza glabra). These herbs are traditionally used to support Pranavaha Srotas (respiratory system) and promote comfortable breathing. Vaasa, Kantkari, Bharangi, and Mulethi have traditionally been valued for their supportive role in respiratory conditions, while Shirish is recognized in Ayurveda for its use in respiratory and allergic disorders.

Dosage: 1 teaspoonful twice a day with lukewarm water.

5. Boswellia Curcumin

It is a herbal combination containing Shallaki (Boswellia serrata) and Curcumin (Curcuma longa), two botanicals traditionally valued for their anti-inflammatory and antioxidant properties. In hepatopulmonary syndrome, chronic liver dysfunction is associated with inflammatory and vascular changes that contribute to abnormal dilatation of pulmonary blood vessels and impaired oxygenation. Shallaki contains boswellic acids, while curcumin provides curcuminoids that have been studied for their ability to modulate inflammatory and oxidative pathways. Therefore, this combination may offer supportive antioxidant and anti-inflammatory benefits in individuals with chronic liver disease.

Dosage: 1 capsule twice a day with plain water after meals.

6. Vasaka Capsules

These capsules containing Vasaka (Adhatoda vasica), are traditionally used in Ayurveda to support the Pranavaha Srotas (respiratory system). Vasaka is known for its bioactive alkaloid vasicine and has traditionally been used for supporting healthy respiratory function, particularly in conditions associated with cough, mucus accumulation, and breathing discomfort. In hepatopulmonary syndrome, respiratory symptoms may occur because abnormal pulmonary vascular changes interfere with efficient oxygenation. Vasaka may therefore be considered as a supportive respiratory herb for maintaining comfortable breathing and overall pulmonary function.

Dosage: 2 capsules twice a day with plain water after meals.

Conclusion

Hepatopulmonary syndrome can substantially affect individuals with chronic liver disorders by compromising oxygenation and gradually limiting physical capacity. Early recognition of respiratory changes is important, particularly in patients with advanced hepatic disease or portal hypertension. Management should address the underlying liver condition, maintain adequate oxygenation, and provide regular clinical monitoring. Ayurvedic approaches may be explored as complementary support for liver and respiratory health under professional supervision. A coordinated, individualized approach can help reduce complications, improve functional status, and support better long-term outcomes.