Category: Low Immunity

Herbal Remedies of Retinopathy of Prematurity (ROP) – Causes, Symptoms, Diagnosis & Treatment

Abstract

Retinopathy of Prematurity (ROP) is a potentially blinding eye disorder that primarily affects premature infants with low birth weight. It occurs due to the abnormal development of retinal blood vessels before they have fully matured. In severe cases, the abnormal blood vessels can bleed, cause retinal scarring, or lead to retinal detachment, resulting in partial or complete vision loss. Advances in neonatal care have improved the survival of premature infants, but the incidence of ROP has also increased. Early screening, timely diagnosis, and appropriate treatment are essential to prevent permanent visual impairment. This article discusses the causes, risk factors, symptoms, stages, diagnosis, complications, treatment, prevention, and Ayurvedic perspective on Retinopathy of Prematurity.
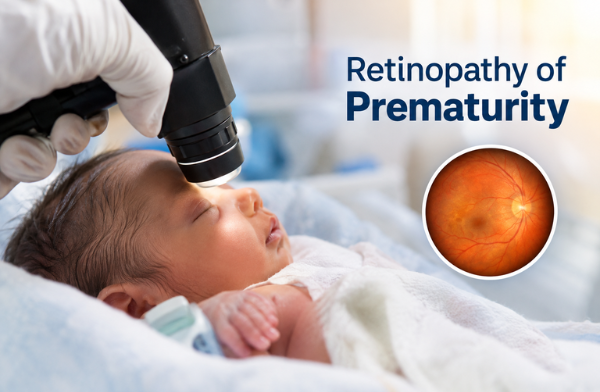
Retinopathy of Prematurity

Quick Facts About Retinopathy of Prematurity (ROP)

  • Retinopathy of Prematurity (ROP) is an eye disease affecting premature infants.
  • It develops due to abnormal growth of retinal blood vessels.
  • Premature babies born before 31 weeks are at the highest risk.
  • Low birth weight is one of the major risk factors.
  • Most mild cases resolve without treatment.
  • Severe ROP may cause retinal detachment and blindness.
  • Both eyes are usually affected, although severity may differ.
  • Regular eye screening is essential for premature infants.
  • Early treatment significantly improves visual outcomes.
  • Laser therapy and anti-VEGF injections are common treatment options.

Global Statistics of Retinopathy of Prematurity (ROP)

  • Approximately 15 million babies are born prematurely each year worldwide.
  • Around 30–40% of very premature infants develop some degree of ROP.
  • Approximately 5–10% of affected infants require treatment.
  • ROP remains one of the leading causes of preventable childhood blindness.
  • The incidence is highest among infants born before 31 weeks of gestation or weighing less than 1500 grams.
  • Improved neonatal survival has increased the number of infants at risk for ROP.
  • Early screening programs have significantly reduced blindness due to ROP.

Introduction

Retinopathy of Prematurity (ROP) is a disorder of retinal vascular development that occurs in premature infants. During normal fetal development, retinal blood vessels continue to grow until full-term birth. When a baby is born prematurely, this process is interrupted, resulting in abnormal blood vessel growth within the retina. These fragile vessels may leak, bleed, or form scar tissue, which can pull on the retina and eventually cause retinal detachment. The severity of ROP ranges from mild disease that resolves spontaneously to advanced stages requiring urgent treatment. Early diagnosis through regular ophthalmic screening plays a crucial role in preserving vision.

Causes of Retinopathy of Prematurity (ROP)

Retinopathy of Prematurity develops because the retinal blood vessels are not fully developed at the time of premature birth. After birth, these immature blood vessels may stop growing normally and later begin to grow abnormally, leading to retinal damage.

Common causes include

  • Premature birth before retinal blood vessels are fully developed
  • Interrupted retinal vascular development
  • Abnormal growth of fragile retinal blood vessels
  • Exposure to high concentrations of supplemental oxygen
  • Fluctuations in blood oxygen levels
  • Immature retinal tissue
  • Poor retinal blood circulation
  • Increased production of vascular endothelial growth factor (VEGF)
  • Oxidative stress affecting retinal cells
  • Neonatal medical complications requiring intensive care

Risk Factors of Retinopathy of Prematurity (ROP)

Although prematurity is the primary risk factor, several maternal and neonatal conditions can further increase the likelihood of developing Retinopathy of Prematurity. The risk becomes significantly higher in infants who are extremely premature or have very low birth weight.

  • Birth before 31 weeks of gestation
  • Birth weight below 1500 grams
  • Extremely low birth weight (<1000 grams)
  • Prolonged oxygen therapy
  • Mechanical ventilation
  • Respiratory distress syndrome
  • Sepsis (bloodstream infection)
  • Multiple blood transfusions
  • Anemia
  • Poor postnatal weight gain
  • Twin or multiple pregnancies
  • Intraventricular hemorrhage
  • Apnea of prematurity
  • Neonatal cardiac disorders

Symptoms of Retinopathy of Prematurity (ROP)

ROP usually does not produce visible symptoms in the early stages. Therefore, routine eye screening is essential for premature infants.

In advanced stages, symptoms may include:

  • Abnormal eye movements
  • White appearance of the pupil (Leukocoria)
  • Crossed eyes (Strabismus)
  • Poor visual tracking
  • Reduced visual response
  • Nystagmus (involuntary eye movements)
  • Severe vision impairment
  • Blindness in advanced cases

Stages of Retinopathy of Prematurity (ROP)

ROP is classified into five stages according to disease severity.

Stage 1 Mild ROP

A thin demarcation line develops between vascularized and non-vascularized retina. Most cases resolve without treatment.

Stage 2 Moderate ROP

The demarcation line becomes elevated, forming a ridge. Careful monitoring is required.

Stage 3 Severe ROP

Abnormal blood vessels grow from the ridge into the vitreous. This stage often requires treatment.

Stage 4 Partial Retinal Detachment

Scar tissue pulls the retina away from the back of the eye, causing partial retinal detachment.

Stage 5 – Total Retinal Detachment

Complete retinal detachment occurs, resulting in severe visual impairment or permanent blindness.

Types of Retinopathy of Prematurity (ROP)

Type 1 ROP

This is severe ROP requiring immediate treatment because of the high risk of vision loss.

Type 2 ROP

This form is less severe and usually requires close observation rather than immediate treatment.

Aggressive Posterior Retinopathy of Prematurity (AP-ROP): This is a rapidly progressive and severe form affecting the posterior retina. It can quickly lead to blindness if untreated.

Diagnosis of Retinopathy of Prematurity (ROP)

Early diagnosis is crucial to prevent permanent vision loss.

Diagnostic methods include:

  • Comprehensive retinal examination using indirect ophthalmoscopy
  • Dilated eye examination
  • Digital retinal imaging
  • Wide-field retinal photography
  • Follow-up retinal examinations based on disease progression

Complications of Retinopathy of Prematurity (ROP)

If left untreated, ROP may result in several long-term eye problems.

Complications include:

  • Retinal detachment
  • Permanent vision loss
  • Blindness
  • High myopia (severe nearsightedness)
  • Strabismus
  • Amblyopia (lazy eye)
  • Glaucoma
  • Cataracts
  • Nystagmus
  • Recurrent retinal problems later in life

Prevention of Retinopathy of Prematurity (ROP)

Although premature birth cannot always be prevented, the risk of severe ROP can be reduced.

Preventive measures include:

  • Appropriate prenatal care
  • Prevention of preterm birth whenever possible
  • Careful monitoring of oxygen therapy
  • Maintaining stable oxygen saturation levels
  • Proper neonatal intensive care
  • Good nutritional support
  • Timely retinal screening
  • Early referral to pediatric ophthalmologists
  • Prompt treatment when indicated

Ayurvedic Aspect of Retinopathy of Prematurity (ROP)

Retinopathy of Prematurity is not directly described in classical Ayurvedic texts. However, based on its pathology involving impaired retinal nourishment, defective vascular development, and vision impairment, it can be understood under disorders affecting Drishti (Vision) and Rakta Dhatu (Blood Tissue). According to Ayurveda, healthy vision depends upon balanced Pitta Dosha, particularly Alochaka Pitta (Type of Pitta responsible for Vision), along with proper nourishment of Rasa Dhatu (Circulatory Fluids), Rakta Dhatu (Blood Tissue), and Majja Dhatu (Bone Marrow). Premature infants have immature body tissues (Dhatu Aparipakvata), making them more susceptible to developmental disorders. Disturbance of Vata Dosha due to premature birth may interfere with normal tissue development and circulation, while vitiated Pitta and Rakta (Blood Tissue) may contribute to vascular abnormalities. Management in Ayurveda focuses on promoting tissue nourishment (Dhatu Poshana), maintaining Dosha balance, supporting overall growth and strengthening ocular health through appropriate Rasayana therapy under expert supervision.

Herbs Beneficial for Eye Health

Ayurveda describes several herbs that help maintain healthy vision by nourishing the eye tissues, balancing the doshas, and protecting the eyes from oxidative stress. The following herbs are traditionally valued for supporting overall eye health.

Amalaki (Emblica officinalis)

Amalaki is one of the richest natural sources of vitamin C and powerful antioxidants. It helps protect retinal cells from oxidative damage, supports healthy blood circulation to the eyes, and nourishes the ocular tissues. In Ayurveda, it balances all three doshas, especially Pitta, and is widely used in formulations for maintaining healthy vision.

Yashtimadhu (Glycyrrhiza glabra)

Yashtimadhu possesses potent anti-inflammatory and antioxidant properties that help protect delicate eye tissues from oxidative stress. It supports tissue healing and may help reduce irritation and inflammation affecting the eyes. Ayurvedically, it nourishes the body’s tissues (Dhatus) and promotes overall ocular health.

Brahmi (Bacopa monnieri)

Brahmi is a renowned Medhya Rasayana that supports the health of the nervous system, including the optic nerve. Its antioxidant activity helps protect retinal cells from free radical damage while improving microcirculation. It also helps reduce oxidative stress that may contribute to age-related eye disorders.

Shatavari (Asparagus racemosus)

Shatavari is a nourishing Rasayana herb that promotes healthy tissue regeneration and supports overall vitality. Its antioxidant properties help protect eye tissues from oxidative injury and support cellular nourishment. It also helps maintain the balance of Pitta Dosha, which plays an important role in healthy vision.

Guduchi (Tinospora cordifolia)

Guduchi is well known for its immunomodulatory and antioxidant effects. It helps protect retinal tissues against oxidative damage, supports healthy circulation, and promotes tissue repair. In Ayurveda, it is considered a rejuvenating herb that strengthens the body’s natural defense mechanisms and supports eye health.

Haritaki (Terminalia chebula)

Haritaki is valued for its detoxifying and rejuvenating properties. It helps remove metabolic waste, improves microcirculation, and supports healthy tissue nutrition, including the eyes. As one of the three fruits in Triphala, it contributes to maintaining healthy vision and overall ocular function.

Bibhitaki (Terminalia bellirica):

Bibhitaki possesses antioxidant and anti-inflammatory properties that help protect the eyes from oxidative stress. It supports healthy circulation and contributes to maintaining the integrity of ocular tissues. In Ayurveda, it is considered beneficial for balancing Kapha Dosha and promoting eye health.

Triphala (Terminalia chebula, Terminalia bellirica, and Emblica officinalis)

Triphala is a classical Ayurvedic combination widely recognized for promoting eye health. It is rich in antioxidants that help protect retinal tissues from oxidative damage while supporting healthy circulation and tissue nourishment. Traditionally, Triphala is used to maintain clear vision and support long-term ocular wellness.

Saffron (Crocus sativus)

Saffron contains bioactive compounds such as crocin and crocetin, which exhibit strong antioxidant and neuroprotective properties. These constituents help support retinal function, improve blood flow to the eyes, and protect photoreceptor cells from damage. Traditionally, saffron has been valued for maintaining healthy vision and supporting overall eye function.

Significance of Shiro Pichu in Retinopathy of Prematurity (ROP)

  • Calms Vata Dosha: Shiro Pichu is traditionally used in Ayurveda to pacify aggravated Vata, which is associated with nervous system balance.
  • Supports nervous system nourishment: The medicated oil applied on the head may help nourish and relax the nervous system.
  • Promotes healthy circulation: It may support proper blood circulation in the head and eye region.
  • Provides relaxation: Shiro Pichu is known for its calming effect, which may help reduce stress and promote overall comfort.
  • Supports ocular nourishment: In Ayurvedic practice, it is considered beneficial for maintaining the nourishment of eye tissues.
  • Complementary care: In ROP, Shiro Pichu may be used only as supportive Ayurvedic therapy under professional guidance and should not replace regular pediatric ophthalmic monitoring or standard medical treatment.

Herbal Remedies by Planet Ayurveda for Retinopathy of Prematurity (ROP)

Planet Ayurveda is a renowned Ayurvedic company committed to offering authentic herbal formulations prepared from standardized extracts and pure natural ingredients. Based on the ancient wisdom of Ayurveda, Planet Ayurveda focuses on holistic wellness by promoting balance within the body and supporting overall health naturally. Its formulations are carefully designed to nourish body tissues, maintain healthy circulation, and support the proper functioning of various organs, including the eyes. By combining traditional Ayurvedic principles with modern quality standards, Planet Ayurveda aims to provide safe and effective herbal support for individuals seeking natural wellness solutions.

Following are the remedies for Retinopathy of Prematurity (ROP):

  1. Chandraprabha Vati
  2. Punarnavadi Kashayam
  3. Sri Anu Thailam
  4. Arvindasav

Product Description

Chandraprabha Vati

Chandraprabha Vati is a classical Ayurvedic formulation traditionally used to support overall metabolism, healthy circulation, and tissue nourishment. It contains herbs such as Guggul (Commiphora mukul), Shilajit (Asphaltum punjabianum), Haritaki (Terminalia chebula), Bibhitaki (Terminalia bellirica), Amalaki (Emblica officinalis), etc. In the context of Retinopathy of Prematurity, it may be considered from an Ayurvedic perspective as a supportive remedy for maintaining systemic balance and promoting proper nourishment of body tissues, including those associated with eye health.

Dosage: 1 tablet once daily, crush and mix with syrup.

Punarnavadi Kashayam

Punarnavadi Kashayam is a classical Ayurvedic decoction traditionally used to support healthy circulation, fluid balance, and tissue nourishment. It contains herbs such as Punarnava (Boerhavia diffusa), Mustak (Cyperus rotundus), Ginger (Zingiber officinale) etc. In the context of Retinopathy of Prematurity, it may be considered from an Ayurvedic perspective as a supportive remedy for maintaining healthy blood circulation and nourishing delicate tissues, including those associated with eye health.

Dosage: 5 ml once daily.

Sri Anu Thailam

Sri Anu Thailam is a classical Ayurvedic medicated oil traditionally used in Nasya therapy to support the health of the head, sense organs, and nervous system. It contains herbs such as Jivanti (Leptadenia reticulata), Bala (Sida cordifolia), Daruharidra (Berberis aristata), Yashtimadhu (Glycyrrhiza glabra), etc. In the context of Retinopathy of Prematurity, it may be considered from an Ayurvedic perspective as a supportive remedy for nourishing the head and eye region and maintaining the balance of Vata and Pitta doshas.

Method of Use: Put 1 drop in each nostril.

Arvindasav

Arvindasav is a classical Ayurvedic formulation traditionally used to support the healthy growth, digestion, and overall nourishment of infants and children. It contains herbs such as Kamal (Nelumbo nucifera), Bala (Sida cordifolia), Nelophar (Nymphaea stellata), etc. In the context of Retinopathy of Prematurity, it may be considered from an Ayurvedic perspective as a supportive remedy for promoting overall nourishment, strength, and healthy tissue development in premature infants.

Dosage: 5 ml twice daily.

Note: Retinopathy of Prematurity (ROP) is a serious eye condition that requires regular monitoring by a pediatric ophthalmologist. The Ayurvedic formulations mentioned above are intended only as supportive measures to promote overall nourishment, circulation, and ocular health from an Ayurvedic perspective. They should be used strictly under the supervision of a qualified Ayurvedic physician, especially in premature infants. These remedies are not a substitute for timely ophthalmic screening, laser therapy, anti-VEGF injections, or any other standard medical treatment recommended by the treating specialist.

Conclusion

Retinopathy of Prematurity is a delicate condition associated with abnormal retinal vascular development in premature infants. Early diagnosis and timely medical intervention remain the most important factors in preventing permanent visual impairment. Ayurveda approaches this condition by emphasizing Dhatu Poshana (tissue nourishment), Dosha balance, and strengthening of ocular tissues. Planet Ayurveda’s herbal formulations, along with supportive therapies such as Shiro Pichu, may help maintain overall health, circulation, and eye nourishment when used under expert guidance. An integrated approach combining regular pediatric ophthalmic care with appropriate Ayurvedic support may contribute to better overall well-being and healthy development in infants affected by ROP.
Herbal Remedies of Steven Johnson Syndrome? – Causes, Symptoms, Diagnosis & Treatment

Abstract

Stevens-Johnson Syndrome (SJS) is a rare but severe immune-mediated disorder that primarily affects the skin and mucous membranes. It is most commonly triggered by certain medications or infections and is considered a medical emergency because of its rapid progression and potentially life-threatening complications. The condition begins with flu-like symptoms, followed by painful skin rashes, blistering, and peeling of the skin, often involving the mouth, eyes, and genital region. Prompt diagnosis, immediate withdrawal of the causative drug, hospitalisation, and supportive care are essential for improving outcomes. Ayurveda does not describe Stevens-Johnson Syndrome as a distinct disease entity; however, its clinical manifestations resemble conditions arising from aggravated Pitta and vitiated RaktaDhatu (Blood Tissue) associated with severe inflammatory skin disorders. This article explores the causes, symptoms, diagnosis, conventional management, complications, preventive measures, and Ayurvedic insights into supporting recovery while emphasising the importance of emergency medical care.

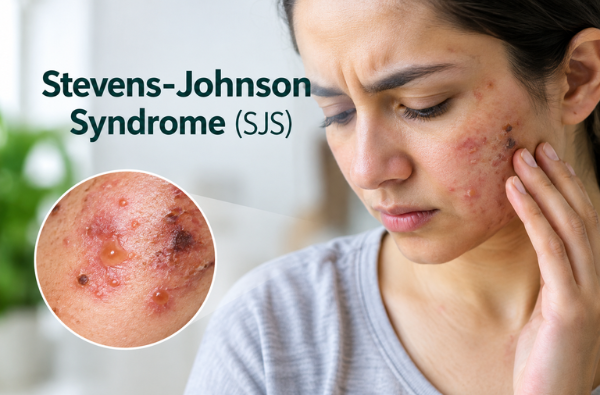
Steven Johnson Syndrome

Introduction

Stevens-Johnson Syndrome (SJS) is one of the most serious dermatological emergencies encountered in clinical practice. Although uncommon, it requires immediate medical attention because it can progress rapidly and involve multiple organ systems. The syndrome causes widespread damage to the skin and mucous membranes, leading to painful blisters, skin peeling, and an increased risk of infections due to loss of the protective skin barrier. SJS may develop in individuals of any age but is more frequently associated with reactions to medications such as antibiotics, anticonvulsants, pain relievers, and certain drugs used for gout. Infections, particularly viral infections, may also act as triggers. Early recognition of warning signs and discontinuation of the offending medication are critical steps in reducing disease severity and preventing complications.

Etiology and High-Risk Triggers

The primary driver of Stevens-Johnson Syndrome is an idiosyncratic, T-cell-mediated hypersensitivity reaction. Unlike typical dose-dependent adverse drug reactions, SJS occurs independently of the quantity of the offending agent ingested. Medications are implicated in over 80% of adult cases.

Common Pharmacological Culprits

  • Anticonvulsants: Phenytoin, carbamazepine, phenobarbital, and lamotrigine.
  • Antimicrobials:Cotrimoxazole and other sulfonamide antibiotics, penicillins, and cephalosporins.
  • Allopurinol: A xanthine oxidase inhibitor frequently prescribed for gout and hyperuricemia.
  • Oxicam NSAIDs:Piroxicam and meloxicam.

Non-Drug Triggers

While medications dominate the etiological landscape, infectious agents serve as crucial triggers, particularly in pediatric populations. Mycoplasma pneumoniae is the most well-documented infectious cause, followed by viral pathogens such as Herpes Simplex Virus (HSV), Cytomegalovirus (CMV), and Influenza. In rare instances, vaccination, malignancy, or idiopathic origins can initiate the cascade.

Pathophysiology and Immunological Cascade

The underlying mechanism of SJS centres on widespread, programmed cell death (apoptosis) of keratinocytes, the primary cell type in the epidermis. This destruction is driven by a cytotoxic T-lymphocyte (CTL) and Natural Killer (NK) cell response directed against drug-modified keratinocyte surface antigens. The process begins when a drug or its metabolite binds to specific Human Leukocyte Antigens (HLA) presented on host cells. This interaction triggers a massive release of cytotoxic molecules:

Granulysin

A key cytolytic protein secreted by CTLs and NK cells. Granulysin levels in blister fluid correlate directly with the severity of the disease. It acts independently of direct cell-to-cell contact, diffusing through tissue to destroy keratinocytes en masse.

Fas-Fas Ligand (FasL) Pathway

The interaction between Fas (a receptor on keratinocytes) and FasL (expressed on activated T-cells) induces an intracellular signalling cascade that forces the skin cells to undergo rapid apoptosis.

Perforin and Granzyme B

These molecules form pores in the target cell membranes, allowing granzymes to enter and cleave intracellular proteins, inducing cellular self-destruction.

As the connections between keratinocytes (desmosomes) dissolve, the epidermis detaches cleanly from the underlying dermis, leading to subepidermal blistering and shedding.

Clinical Progression and Manifestations

The clinical course of Stevens-Johnson Syndrome is traditionally divided into distinct phases, each requiring vigilant clinical monitoring.

The Prodromal Phase

Before any cutaneous changes occur, patients typically experience a 1-to-3-day prodrome that mimics a severe viral illness. Symptoms include high fever, malaise, sore throat, persistent cough, rhinitis, and generalised myalgia. This phase is frequently misidentified, leading patients to self-medicate with more NSAIDs or antibiotics, inadvertently exacerbating the condition.

Cutaneous Eruptions

The rash begins as poorly defined, flat, erythematous (red) or purpuric (purple) macules, often displaying a “targetoid” or atypical target-like appearance. These lesions typically appear first on the face and trunk before spreading symmetrically to the limbs. Within hours to days, the centers of these macules become vesicular or bullous, coalescing into large sheets of detached skin. A hallmark clinical sign is a positive Nikolsky Sign, where applying gentle lateral pressure to the surface of normal-appearing skin causes the upper layer to slide off, exposing a raw, weeping dermis.

Mucosal Involvement

Mucosal erosion occurs in over 90% of SJS patients and often precedes the skin rash. It simultaneously affects multiple sites:

  • Oral: Severe, painful hemorrhagic crusts on the lips, buccal mucosa, and tongue, rendering eating, drinking, and swallowing nearly impossible.
  • Ocular: Intense conjunctivitis, chemosis (swelling of the conjunctiva), corneal ulcerations, and pseudomembranous sheets that can lead to permanent vision loss if left untreated.
  • Urogenital: Painful erosions of the vulva, vagina, or urethral meatus, leading to urinary retention.

How Does Stevens-Johnson Syndrome Affect the Body?

The destruction of skin cells causes a breakdown of the protective skin barrier. As a result:

  • Fluid loss increases.
  • Electrolyte imbalance develops.
  • Bacterial infections become more likely.
  • Body temperature regulation is impaired.
  • Healing becomes prolonged.

Because multiple mucous membranes are affected, eating, drinking, speaking, and vision may become difficult.

The SJS-TEN Spectrum and Prognosis

Stevens-Johnson Syndrome is part of a continuous disease spectrum, categorised entirely by the extent of epidermal detachment relative to total body surface area (TBSA):

  • Stevens-Johnson Syndrome (SJS): Epidermal detachment involving less than 10% of TBSA.
  • SJS/TEN Overlap: Epidermal detachment involving between 10% and 30% of TBSA.
  • Toxic Epidermal Necrolysis (TEN):Epidermal detachment involving greater than 30% of TBSA.

To determine prognosis, clinicians utilise the SCORTEN scale, a validated clinical scoring system. Points are assessed based on seven independent risk factors measured within the first 24 hours of admission: age over 40, presence of malignancy, heart rate greater than 120 bpm, initial detached TBSA greater than 10%, serum urea greater than 10 mmol/L, serum glucose greater than 14 mmol/L, and serum bicarbonate less than 20 mEq/L. Higher scores indicate an escalating mortality risk, primarily driven by hypovolemic shock, acute respiratory distress syndrome (ARDS), and multi-organ failure secondary to sepsis.

Risk Factors

Certain individuals are more susceptible to developing SJS.
Important risk factors include:

  • Previous episode of SJS
  • Family history of SJS
  • Specific genetic markers (such as HLA-B*1502 in some Asian populations receiving carbamazepine)
  • HIV infection
  • Autoimmune disorders
  • Weakened immune system
  • Multiple medication use

Complications

Potential complications include:

  • Secondary bacterial infection
  • Sepsis
  • Pneumonia
  • Permanent skin scarring
  • Pigment changes
  • Chronic dry eyes
  • Corneal ulcers
  • Vision loss
  • Nail abnormalities
  • Genital scarring
  • Respiratory complications

In severe cases, SJS can become life-threatening.

Diagnosis

Diagnosis is primarily clinical. Investigations may include:

  • Detailed medication history
  • Physical examination
  • Skin biopsy
  • Complete blood count
  • Liver function tests
  • Kidney function tests
  • Electrolyte assessment
  • Culture if infection is suspected

A skin biopsy confirms epidermal necrosis and helps differentiate SJS from other blistering disorders.

Advanced Biomedical Management

Managing SJS requires a multi-disciplinary approach, ideally within an intensive care unit (ICU) or a specialised burn centre.

Immediate Discontinuation of the Offending Agent

The single most critical prognostic factor is the prompt identification and withdrawal of the causative drug. Delays in stopping the trigger medication significantly increase mortality rates.

Supportive Care

Supportive therapy mimics severe burn management:

  • Fluid and Electrolyte Balance: Intravenous fluid resuscitation using crystalloids must be carefully titrated to compensate for massive transdermal fluid loss without causing pulmonary edema.
  • Wound Management: Non-adherent, sterile dressings are applied gently. Debridement is typically avoided to protect the viable dermal bed.
  • Ocular Care: Aggressive lubrication, topical antibiotics, and early amniotic membrane transplantation are used to prevent long-term blindness and symblepharon (adhesion of the eyelid to the eyeball).
  • Nutritional Support: High-calorie, high-protein enteral nutrition via a nasogastric tube is introduced early to counter the hypermetabolic state, especially when oral intake is compromised.

Pharmacological Modulations

Systemic immunomodulatory therapies remain debated but are widely utilised to arrest the necrotic cascade:

  • Corticosteroids: High-dose pulse therapy (e.g., methylprednisolone) within the first 24–48 hours can suppress the initial inflammatory storm.
  • Intravenous Immunoglobulin (IVIG): Contains antibodies that can block the Fas-mediated apoptotic pathway, limiting skin detachment.
  • Cyclosporine: A potent T-cell inhibitor that has demonstrated efficacy in reducing mortality by arresting CTL-driven keratinocyte destruction.
  • TNF-alpha Inhibitors:Etanercept has emerged as a promising option due to its rapid action in lowering systemic and local inflammatory markers.

Recovery and Long-Term Outlook

Most patients require several weeks for skin healing.

However, long-term problems may persist, including:

  • Dry eyes
  • Skin discoloration
  • Scarring
  • Nail deformities
  • Photosensitivity
  • Emotional distress
  • Chronic pain

Regular follow-up with dermatologists and ophthalmologists is often necessary.

How Can Stevens-Johnson Syndrome Be Prevented?

Preventive measures include:

  • Avoiding the causative medication permanently.
  • Wearing a medical alert bracelet.
  • Informing healthcare providers about previous drug allergies.
  • Genetic testing before starting high-risk medications in susceptible populations.
  • Maintaining updated medical records.

Patients who have experienced SJS should never re-expose themselves to the triggering drug because recurrence may be more severe.

Ayurvedic Perspective on Stevens-Johnson Syndrome

In contemporary Ayurvedic science, Stevens-Johnson Syndrome can be understood through a multi-tiered framework encompassing Asatmya (unwholesome/allergic responses), GaraVisha (xenobiotic/chemically induced toxicosis), and an acute, fulminant manifestation of Rakta-Pitta (blood-bile systemic perversion).

The Concept of Asatmya (Unwholesome) and Satmya (Wholesome)

Ayurveda describes Satmya (wholesome compatibility) as substances and practices that are naturally suited to an individual’s constitution (Prakriti). In contrast, an adverse drug reaction represents a severe state of Asatmya (incompatibility) or ViruddhaPratikriya (adverse response to an incompatible substance). When an incompatible substance (AsatmyaDravya – incompatible drug or substance) enters the body, it disturbs the natural balance of the Tridosha (Vata, Pitta, and KaphaDoshas), leading to widespread systemic dysfunction.

Pathogenesis through GaraVisha (Artificial Poisoning) and DushiVisha (Latent Toxicity)

From an Ayurvedic perspective, certain synthetic drugs that trigger severe hypersensitivity reactions can be conceptually understood under GaraVisha (artificially prepared toxins) and DushiVisha (latent or cumulative toxins). These toxic substances initially vitiate the Rasa Dhatu (plasma and lymphatic tissue) and RaktaDhatu (blood tissue), disrupting their normal physiological functions. As the toxins spread through the body, they produce DhatuShaithilya (weakening and loss of structural integrity of body tissues), resulting in fragile skin and separation between skin layers, which clinically resembles the positive Nikolsky sign seen in Stevens-Johnson Syndrome.

Fulminant Rakta-Pitta (Acute Blood and Pitta Disorder) with Kushtha (Severe Skin Disease) Manifestation

The principal pathology involves a sudden and intense aggravation of Pitta Dosha (the bioenergy governing heat, metabolism, and transformation), particularly Bhrajaka Pitta (the subtype of Pitta responsible for skin metabolism and complexion), along with severe vitiation of RaktaDhatu (blood tissue). This creates a SannipatajaAvastha (a critical condition involving all three Doshas, predominantly Pitta and Rakta). Excessive internal heat damages the Tvacha (skin) and progressively affects its deeper layers, resulting in extensive redness, blister formation, burning sensation, ulceration, and tissue necrosis. The severe involvement of the oral and ocular mucosa resembles an aggravated form of MukhaPaka (ulcerative inflammation of the oral cavity) and Netra Daha (burning and inflammation of the eyes).

Depletion of Ojas (Vital Essence)

Extensive skin peeling, fluid loss, and systemic inflammation ultimately lead to the depletion of Ojas (the vital essence responsible for immunity, tissue strength, and overall vitality). In Ayurveda, Ojas maintains the integrity and cohesion of body tissues; therefore, its depletion results in weakened immunity, delayed healing, and increased susceptibility to AgantujaVyadhi (externally acquired diseases and infections). This concept closely parallels the modern understanding of secondary bacterial infections and sepsis that may develop following extensive skin barrier loss in Stevens-Johnson Syndrome.

Integrated Management and Long-Term Rehabilitation

While the acute, life-threatening phase of SJS requires immediate modern biomedical intensive care, an integrated approach incorporating Ayurvedic principles can aid long-term recovery and rehabilitation once the patient stabilises. During the acute phase, direct application of heavy formulations is contraindicated. Instead, management centres on maintaining a cool environment and supporting the skin. As the patient transitions out of danger, gentle therapies focus on clearing residual toxins (Visha-Nirharana) and restoring tissue integrity.

Rakta-Prasadana (Blood Purification)

Administering mild, bitter (Tikta) and sweet (Madhura) formulations helps soothe the aggravated Pitta and Rakta. Herbs such as Sariva (Hemidesmusindicus), Manjistha (Rubiacordifolia), and Guduchi (Tinosporacordifolia) support the body’s natural healing and detoxification processes.

Tvachya and Ropana (Skin Regeneration)

To assist epidermal healing, thin applications of cooled JatyadiGhrita or ShatadhautaGhrita (one-hundred-times-washed clarified butter) can be applied to closed, healing lesions. These preparations provide essential fatty acids and cooling moisture to reduce scarring and itching.

Ojo-Vardhaka (Immune Reconstruction)

Once digestion (Agni) returns to normal, mild rejuvenative agents (Rasayana) like Amalaki (Emblica officinalis) are introduced to support the recovery of Ojas (Immunity) and strengthen the skin barrier against future hyper-responsiveness.

Ayurvedic Principles That May Support Recovery

Following the acute phase and with medical approval, Ayurvedic principles may focus on restoring tissue health and promoting systemic balance. Supportive measures may include:

  • Maintaining a light, easily digestible diet.
  • Avoid excessively spicy, fried, fermented, and processed foods.
  • Consuming cooling and nourishing foods according to individual needs.
  • Supporting digestive fire without aggravating Pitta.
  • Ensuring adequate hydration.
  • Following physician-guided skin care during healing.

Herbal support should only be initiated after stabilisation and under the guidance of a qualified Ayurvedic physician, considering ongoing medications and overall health status.

Lifestyle Recommendations During Recovery

Recovery requires patience and comprehensive care. Patients are encouraged to:

  • Get adequate rest.
  • Protect healing skin from direct sunlight.
  • Avoid self-medication.
  • Follow prescribed wound care instructions.
  • Maintain excellent hydration.
  • Consume a balanced diet rich in protein and vitamins.
  • Attend regular follow-up appointments.
  • Seek psychological support if emotional distress develops.

Herbal Remedies for Stevens-Johnson Syndrome by Planet Ayurveda

Planet Ayurveda is dedicated to making traditional Ayurvedic healthcare accessible worldwide through high-quality herbal formulations and personalised wellness guidance. Inspired by the classical Ayurvedic texts, the company manufactures herbal products free from artificial colours, preservatives, fillers, and synthetic chemicals. With a strong emphasis on purity, authenticity, and holistic healing, Planet Ayurveda empowers individuals to maintain optimal health naturally while supporting long-term physical and mental wellness. In this article, we will discuss some herbal formulations that are effective in the management of Stevens-Johnson Syndrome.

  • KaishoreGuggul
  • GandhakRasayan
  • Manjishtha capsules
  • Gleaming Skin, Hair, Nails Formula
  • Chopchinichurna

Product Description

1. KaishoreGuggul

Kaishore Guggul is a classical Ayurvedic formulation traditionally indicated for disorders involving vitiated Pitta and RaktaDhatu (blood tissue), making it a supportive option during the recovery phase of Stevens-Johnson Syndrome (SJS) under the supervision of a qualified Ayurvedic physician. Its key ingredients, including Guggul (Commiphoramukul), Guduchi (Tinosporacordifolia), Triphala, and Trikatu, help support the body’s natural detoxification processes, maintain healthy inflammatory responses, and promote tissue healing. Guggulsterones contribute to regulating inflammatory pathways, while Guduchi provides immunomodulatory and antioxidant support that may aid recovery from extensive tissue injury. The formulation also supports healthy blood purification and assists in maintaining balanced Pitta Dosha, which is considered central to inflammatory skin disorders in Ayurveda. By supporting wound healing, improving tissue metabolism, and promoting internal balance, KaishoreGuggul may complement conventional care during convalescence.

Dosage: 2 tablets twice daily after a meal with Plain water.

2. GandhakRasayan

Gandhak Rasayan is a classical Ayurvedic formulation prepared from purified sulfur (ShuddhaGandhak) through repeated processing with herbal juices, which enhances its therapeutic properties. In the recovery phase of Stevens-Johnson Syndrome (SJS), it may serve as a supportive formulation by promoting healthy skin regeneration and maintaining the integrity of damaged tissues. Purified sulfur is traditionally regarded as Rasayana (rejuvenative) and Kushtaghna (beneficial in skin disorders), helping restore the balance of RaktaDhatu (blood tissue) and Pitta Dosha, which are considered significantly disturbed in severe inflammatory skin conditions. Its antioxidant and antimicrobial properties may help support natural wound healing and reduce the risk of secondary skin infections. GandhakRasayan also aids tissue nourishment, supports healthy collagen remodelling, and promotes faster recovery of the skin barrier.

Dosage: 2 tablets twice daily after a meal with Plain water.

3. Manjishtha capsules

Manjishtha Capsules by Planet Ayurveda, containing Manjishtha (Rubiacordifolia), may provide supportive care during the recovery phase of Stevens-Johnson Syndrome (SJS) by promoting healthy skin repair and maintaining the balance of RaktaDhatu (blood tissue). The herb is rich in bioactive compounds such as alizarin, purpurin, and anthraquinones, which exhibit antioxidant and anti-inflammatory properties that help protect damaged skin cells from oxidative stress. In Ayurveda, Manjishtha is regarded as one of the foremost RaktaShodhaka (blood-purifying) herbs, helping to clear inflammatory metabolites and support healthy microcirculation to healing tissues. It also assists in maintaining normal skin pigmentation and promotes regeneration of the skin after blistering and peeling. By supporting tissue repair, reducing persistent inflammation, and encouraging healthy wound healing, Manjishtha Capsules may complement recovery and help restore skin integrity.

Dosage: 1 Capsule twice daily after a meal with Plain water.

4. Gleaming Skin, Hair, Nails Formula Capsules

These Capsules by Planet Ayurveda contain Manjistha (Rubiacordifolia), Pit Papda (Fumaria officinalis), Sariva (Hemidesmusindicus), and GhritKumari (Aloe barbadensis), a combination traditionally valued for promoting healthy skin and supporting tissue repair. During the recovery phase of Stevens-Johnson Syndrome (SJS), these herbs may help maintain the balance of Pitta Dosha and RaktaDhatu (blood tissue), which are considered significantly disturbed in severe inflammatory skin disorders. Manjistha supports healthy microcirculation and skin regeneration, while Pit Papda is traditionally used to pacify excess heat and support normal skin physiology. Sariva provides antioxidant and cooling properties that help soothe irritated tissues, and GhritKumari contains polysaccharides that promote hydration, epithelial regeneration, and restoration of the skin barrier. Together, these herbs support the natural healing of damaged skin, help improve tissue nourishment, and encourage healthy recovery following extensive skin inflammation.

Dosage: 1 Capsule twice daily after a meal with Plain water.

5. ChopchiniChurna

It is prepared from Chopchini (Smilax china) and is traditionally valued in Ayurveda for supporting skin health and maintaining the purity of RaktaDhatu (blood tissue). During the recovery phase of Stevens-Johnson Syndrome (SJS), it may help support the body’s natural detoxification processes and promote healthy tissue remodelling after extensive skin damage. Smilax china contains bioactive compounds such as saponins, flavonoids, and polyphenols, which exhibit antioxidant and anti-inflammatory activities that help protect regenerating skin from oxidative stress. The herb is also recognised for supporting connective tissue health and maintaining normal immune function, which may contribute to improved skin recovery.

Dosage: ½ tsp twice daily after a meal with Plain water.

Conclusion

Stevens-Johnson Syndrome is a rare but potentially life-threatening condition that demands immediate medical attention. Most cases are triggered by medications, making early recognition and prompt discontinuation of the offending drug crucial for improving outcomes. Comprehensive hospital-based care remains the cornerstone of treatment, focusing on supportive management, infection prevention, wound care, and preservation of organ function. From an Ayurvedic perspective, the condition reflects profound disturbances of Pitta Dosha and RaktaDhatu, highlighting the importance of restoring internal balance during the recovery phase. While Ayurveda may offer supportive measures to promote tissue healing, digestive health, and overall well-being after stabilisation, it should always complement—not replace—emergency conventional medical treatment. A collaborative, integrative approach under the guidance of qualified healthcare professionals provides the best opportunity for safe recovery and long-term health.