Upadoz / Upadacitinib in IBD: Can JAK1 Inhibition Change the Inflammatory Story?
Abstract
Inflammatory bowel disease (IBD), encompassing ulcerative colitis and Crohn’s disease, involves persistent immune activation and dysregulated cytokine signaling that can lead to recurrent intestinal inflammation and tissue injury. Upadacitinib, marketed as Upadoz, is an oral, selective JAK1 inhibitor that targets intracellular cytokine signaling and interrupts downstream JAK-STAT pathways involved in immune activation. By acting closer to the signaling machinery rather than a single extracellular inflammatory mediator, JAK1 inhibition represents a distinct therapeutic strategy in IBD. Clinical evidence has demonstrated meaningful improvements in clinical remission, endoscopic response, and disease control in moderate-to-severe ulcerative colitis and Crohn’s disease.
Introduction
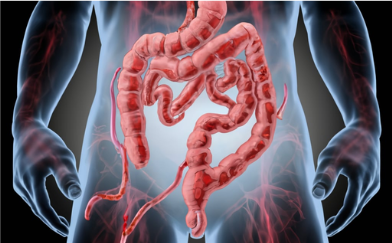
Inflammatory bowel disease (IBD) represents a complex group of chronic intestinal disorders in which persistent immune activation, abnormal cytokine signaling, and disruption of mucosal integrity contribute to ongoing disease activity. Ulcerative colitis and Crohn’s disease differ in their anatomical patterns and pathological characteristics, yet both involve interconnected inflammatory pathways that can sustain intestinal damage and recurrent symptoms. The Janus kinase-signal transducer and activator of transcription (JAK-STAT) pathway occupies an important position in cytokine-mediated immune signaling. JAK1 participates in signaling triggered by several cytokines implicated in intestinal inflammation, making selective JAK1 inhibition an attractive therapeutic approach. Upadacitinib, marketed as Upadoz, is an oral JAK inhibitor with preferential activity against JAK1. By interfering with intracellular phosphorylation and subsequent STAT activation, it can modulate signaling from multiple cytokine pathways rather than targeting a single extracellular mediator. Its oral administration and relatively rapid pharmacological action further distinguish it from several conventional biologic approaches.
Pharmacological Profile of Upadacitinib
Hepatopulmonary syndrome develops mainly as a consequence of chronic liver dysfunction and portal hypertension, which produce abnormal changes in the blood vessels of the lungs. The central abnormality involves excessive widening of small pulmonary blood vessels. This dilatation interferes with the normal movement of oxygen from the air spaces of the lungs into the bloodstream, resulting in reduced arterial oxygen levels. Several liver-related conditions can contribute to the development of HPS.
- Drug class: Upadacitinib is an oral small-molecule Janus kinase (JAK) inhibitor with preferential activity against JAK1.
- Molecular action: It binds to the ATP-binding region of JAK1 and inhibits its kinase activity. This reduces phosphorylation and activation of downstream STAT proteins involved in cytokine-mediated gene transcription.
- Cytokine modulation: JAK1 participates in signaling by several cytokines, including pathways involving interleukin-6, interferons, and other cytokines that contribute to immune regulation. Inhibition therefore influences multiple inflammatory signals simultaneously.
- Pharmacokinetic profile: Upadacitinib is administered orally and is rapidly absorbed, reaching peak plasma concentrations within a few hours. Its pharmacokinetic properties support once-daily administration.
- Metabolism: The drug undergoes hepatic metabolism, predominantly involving CYP3A4, with additional contribution from other metabolic pathways.
- Elimination: Upadacitinib and its metabolites are eliminated through both fecal and urinary routes, with unchanged drug accounting for only a limited proportion of total elimination.
- Half-life: Its effective terminal half-life is approximately 8–14 hours, supporting sustained pharmacological activity with once-daily dosing.
- Therapeutic positioning in IBD: Upadacitinib is used for appropriate patients with moderate-to-severe ulcerative colitis and Crohn’s disease, particularly when conventional or biologic therapies have not provided adequate disease control or are unsuitable.
- Safety considerations: Important monitoring considerations include infections, herpes zoster, hematological abnormalities, liver enzyme changes, lipid alterations, and thromboembolic or cardiovascular risks in susceptible patients.
- Clinical significance: Its oral route, selective JAK1 activity, and ability to modulate intracellular signaling from several cytokine pathways make upadacitinib a distinct targeted option within the expanding therapeutic landscape of IBD.
Upadacitinib: Mechanism of Action in IBD
Upadacitinib is an oral, selective Janus kinase 1 (JAK1) inhibitor that modulates intracellular cytokine signaling involved in immune activation and intestinal inflammation. Its therapeutic activity is based on interference with the JAK-STAT signaling pathway, an important intracellular mechanism through which numerous cytokines regulate immune-cell function. Following cytokine binding to specific cell-surface receptors, receptor-associated JAK enzymes become activated and phosphorylate signal transducer and activator of transcription (STAT) proteins. These phosphorylated STAT proteins subsequently translocate into the nucleus, where they influence transcription of genes involved in inflammatory responses, immune-cell differentiation, proliferation, and survival. Upadacitinib selectively inhibits JAK1, thereby reducing signaling mediated by cytokines that depend substantially on JAK1-containing receptor complexes. In IBD, modulation of JAK1 signaling can affect multiple inflammatory pathways simultaneously rather than neutralizing a single cytokine outside the cell. This pharmacological approach may reduce downstream immune activation and inflammatory gene expression within intestinal tissues.
The Inflammatory Pathways Driving IBD
Inflammatory bowel disease develops through a complex interaction between intestinal immunity, the gut microbiome, epithelial barrier function, and environmental influences. Rather than being driven by one inflammatory molecule, IBD involves several interconnected signaling networks that amplify and sustain inflammation.
Breakdown of the Intestinal Barrier
The intestinal epithelium forms the first protective interface between the body’s immune system and luminal contents. In IBD, impaired epithelial integrity can increase intestinal permeability, allowing microbial products and other luminal antigens to interact more extensively with immune cells. Alterations in tight-junction proteins can further compromise barrier function.
Abnormal Recognition of Intestinal Antigens
The intestinal immune system normally distinguishes harmless dietary and microbial components from potentially harmful signals. In IBD, this regulatory balance becomes disturbed. Pattern-recognition receptors on epithelial and immune cells detect microbial components and activate intracellular inflammatory pathways.
Activation of Innate Immune Responses
Macrophages, dendritic cells, neutrophils, and other innate immune cells participate in the early inflammatory response. Activated macrophages can release inflammatory mediators such as tumor necrosis factor-alpha (TNF-alpha), interleukin-1 beta (IL-1 beta), and interleukin-6 (IL-6).
Dysregulated T-Cell Responses
Adaptive immunity has a major role in maintaining chronic intestinal inflammation. T-helper 1 (Th1) responses and cytokines such as interferon-gamma are particularly relevant to Crohn’s disease.
JAK-STAT Signaling
The Intracellular Communication Hub – The Janus kinase-signal transducer and activator of transcription (JAK-STAT) pathway is one of the major signaling mechanisms involved in this process. Cytokine binding to its receptor activates associated JAK enzymes, which phosphorylate STAT proteins.
From Local Inflammation to Tissue Damage
Persistent inflammatory signaling eventually affects the structural integrity and function of the intestinal mucosa. Repeated immune-cell infiltration and inflammatory mediator release can interfere with epithelial repair. Chronic inflammation can therefore contribute to ulceration, impaired barrier function, fibrosis, stricturing, fistula formation, and other disease complications, particularly in Crohn’s disease.
Can JAK1 Inhibition Change the Inflammatory Story?
Inflammation in inflammatory bowel disease (IBD) is not controlled by a single molecule or one isolated pathway. Several cytokines communicate with immune cells and intestinal tissues at the same time, creating a continuous inflammatory network. This complexity is one reason why controlling IBD can be challenging, particularly in patients with moderate-to-severe disease or inadequate response to previous treatments. Thus, JAK1 inhibition represents a shift from targeting individual inflammatory mediators toward modifying a central intracellular signaling pathway involved in multiple cytokine responses.
Broader inflammatory control
JAK1 participates in signaling from multiple cytokine receptors. Its inhibition can therefore reduce several inflammatory signals simultaneously.
Reduced immune-cell activation
By limiting JAK-STAT signaling, upadacitinib can decrease downstream processes that sustain intestinal inflammation.
Improved disease activity
Reduced inflammatory signaling can help control symptoms and promote improvement in objective measures of intestinal inflammation.
Relevance to difficult-to-treat IBD
Upadacitinib provides an additional treatment option for patients with moderate-to-severe ulcerative colitis or Crohn’s disease, including those with inadequate response to previous therapies.
Rapid and convenient approach
Its oral administration and relatively rapid clinical response add practical advantages to its therapeutic profile.
Potential Impact on Intestinal Inflammation
As inflammatory signaling decreases, several components of the disease process may improve. Reduced immune activation can contribute to lower inflammatory activity within the intestinal mucosa, while improvement in mucosal inflammation may support restoration of intestinal function.
JAK1 Inhibition Is Not Simply About Suppressing Immunity
The therapeutic objective is not to eliminate immune activity. The immune system remains essential for protection against infections and other threats. The goal is to reduce excessive or inappropriate inflammatory signaling while maintaining adequate immune function. This balance is central to understanding both the benefits and safety considerations of JAK1 inhibition.
Dosage and Treatment Considerations of Upadacitinib
Upadacitinib treatment in inflammatory bowel disease follows an induction-maintenance approach, with a higher dose used initially to control active disease and a maintenance regimen used for sustained disease control.
Ulcerative Colitis
The recommended induction dose for adults with moderate-to-severe ulcerative colitis is 45 mg once daily for 8 weeks. The usual maintenance dose is 15 mg once daily. A 30 mg once-daily maintenance dose may be considered in patients with refractory, severe, or extensive disease when clinically appropriate.
Crohn’s Disease
The recommended induction dose for adults with moderate-to-severe Crohn’s disease is 45 mg once daily for 12 weeks. The recommended maintenance dose is 15 mg once daily. A 30 mg once-daily maintenance dose may be considered for patients with refractory, severe, or extensive disease.
Administration
Upadacitinib is taken orally once daily. The extended-release tablet should be swallowed whole and should not be crushed, split, or chewed. It can generally be taken with or without food.
Assessment Before Treatment
Before initiating therapy, patients should be evaluated for active infections and relevant risk factors. Baseline assessment generally includes complete blood count, liver function, lipid profile, tuberculosis screening, and hepatitis evaluation, together with a review of vaccination status and concomitant medications.
Monitoring During Treatment
Regular monitoring is important to assess both therapeutic response and tolerability. Depending on the patient’s clinical condition, this may include: complete blood count, liver enzymes, lipid profile, signs and symptoms of infection, inflammatory markers, and objective assessment of intestinal inflammation when appropriate.
Infection Considerations
Because JAK inhibition modifies immune activity, upadacitinib can increase susceptibility to infections. Particular attention should be given to tuberculosis, herpes zoster, and serious or opportunistic infections. Treatment decisions should be reassessed if a significant infection develops.
Long-Term Treatment
Maintenance therapy requires periodic reassessment of disease control, treatment benefit, and safety. The maintenance regimen should be individualized according to disease severity, therapeutic response, tolerability, and the patient’s overall risk profile.
Ayurveda Insights
From an Ayurvedic perspective, the inflammatory pattern of IBD can be understood through the interaction of Agni, Ama, Dosha imbalance, and impaired Grahani function. Disturbed digestion and metabolism may lead to Ama formation, while aggravated Vata and Pitta can contribute to altered bowel function, intestinal irritation, and inflammatory manifestations. Grahani is considered closely connected with the proper maintenance of digestion and absorption, making its functional disturbance relevant when interpreting chronic gastrointestinal disorders. Although Upadoz / Upadacitinib acts through the modern JAK1 pathway and does not have a direct Ayurvedic equivalent, its role in regulating excessive inflammatory signaling can be viewed alongside the Ayurvedic objective of restoring balance in Dosha, Agni, and Grahani function.
Pathogenesis of Inflammatory Bowel Disease According to Ayurveda
From the Ayurvedic perspective, the pathological progression can be described as a Samprapti involving disturbance of the gastrointestinal tract and subsequent involvement of the Doshas. Initial dietary and lifestyle factors can disturb normal intestinal physiology, followed by vitiation of Vata, Pitta, or their combination according to the individual’s presentation. Vitiated Vata can drive abnormal intestinal movement and pain, whereas aggravated Pitta can intensify intestinal irritation, burning, loose stools, and bleeding. Kapha, when involved, can contribute to excessive mucus and heaviness. With continued Dosha aggravation, these factors affect the functional integrity of Grahani, resulting in impaired retention and elimination of intestinal contents. In advanced or persistent disease, repeated Dosha disturbance can produce deeper involvement of the intestinal tissues, explaining the chronic and relapsing nature of gastrointestinal pathology from an Ayurvedic viewpoint.
Alternatives of Upadicitinib in Management of Inflammatory Bowel Disease by Planet Ayurveda
Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Inflammatory Bowel Disease according to Ayurvedic principles. The herbal formulations are:
- Kutajghan Vati
- Atisaran Mukti
- Pitta Balance
- Vatsakadi Churna
- Arjuna Capsules
- Motion Stop Tablets
- Vasaka Capsules
- Coolstrin A Capsules
- Coolstrin B Capsules
- Aegle Plan Capsules
- Halorhena + Capsules
- Hemostop-B Powder
- Mimosa-Di Capsules
Product description
1. Kutajghan Vati
It contains Kutaja (Holarrhena pubescens), can be considered an Ayurvedic herbal formulation for supporting bowel regulation in gastrointestinal disorders characterized by frequent or loose stools. Kutaja is described in Ayurveda for its Grahi and Kashaya properties, which help support intestinal tone and stool consistency. Its astringent nature may also help maintain the integrity of the intestinal mucosa and reduce excessive intestinal secretions. In the context of IBD, Kutajghan Vati may be incorporated as an adjunctive Ayurvedic approach for managing diarrhea, bowel frequency, and associated gastrointestinal discomfort.
Dosage: 2 tablets two times a day after meals with plain water.
2. Atisaran Mukti
It is an Ayurvedic herbal formulation containing Kutaja (Holarrhena antidysenterica), Bilwa (Aegle marmelos), Saunf (Foeniculum vulgare), Dhaniya (Coriandrum sativum), Nagarmotha (Cyperus scariosus), Anar (Punica granatum), Chhoti Elaichi (Elettaria cardamomum), and Jaiphal (Myristica fragrans). The combination is primarily focused on supporting healthy bowel function and improving stool consistency. Kutaja and Bilwa possess Grahi properties that help regulate excessive intestinal fluid loss, while Nagarmotha and Dhaniya support digestion and reduce gastrointestinal discomfort. Anar provides an astringent action, while Saunf and Elaichi support digestion and ease abdominal uneasiness.
Dosage: 1 capsule two times a day after meals with plain water.
3. Pitta Balance
Pitta Balance is an Ayurvedic formulation comprising Jaharmohra Pishti (natural calcium compound), Kaharawa Pishti (natural calcium compound), Akik Pishti (agate compound), Giloy Satva (Tinospora cordifolia extract), and Mukta Pishti (natural calcium compound derived from pearls). The formulation is intended to support Pitta balance and gastrointestinal comfort, which is relevant when burning sensation, loose stools, and intestinal irritation accompany digestive disturbances. Giloy Satva contributes its Pitta-shamaka and Rasayana properties, while the mineral and gemstone-based Pishtis are traditionally used for their cooling and soothing qualities.
Dosage: 1 capsule twice a day after meals with plain water.
4. Vatsakadi Churna
It is an Ayurvedic herbal formulation containing Kutaja (Holarrhena antidysenterica), Bilva (Aegle marmelos), Saunf (Foeniculum vulgare), Dhaniya (Coriandrum sativum), Anar (Punica granatum), Nagarmotha (Cyperus scariosus), and Jaiphal (Myristica fragrans). The formulation is primarily useful for supporting bowel regulation and digestive function, particularly when loose stools and increased bowel frequency are prominent. Kutaja and Bilva provide Grahi and astringent properties that help maintain healthy stool consistency, while Nagarmotha and Jaiphal support digestion and intestinal function. Saunf and Dhaniya may help relieve bloating and abdominal discomfort.
Dosage: 1 teaspoonful twice a day after meals with plain water.
5. Arjuna Capsules
It contains Arjuna (Terminalia arjuna), can be included as supportive Ayurvedic therapy in the broader management of inflammatory bowel disease (IBD). Arjuna is recognized in Ayurveda for its Kashaya (astringent) and Ropana (tissue-supporting) properties, which may be relevant when intestinal mucosal irritation and weakness accompany chronic bowel disorders. Its antioxidant and anti-inflammatory properties also provide a rationale for supporting tissue protection during persistent inflammatory conditions.
Dosage: 1 capsule twice a day after meals with plain water.
6. Motion Stop Tablets
These contain Kutaja (Holarrhena antidysenterica), Bael (Aegle marmelos), Haldi (Curcuma longa), Anar (Punica granatum), and Nagarmotha (Cyperus scariosus) along with suitable pharmaceutical excipients. The formulation is focused on supporting bowel regulation, particularly when frequent or loose stools are present. Kutaja and Bael possess Grahi and astringent properties that help support healthy stool consistency, while Nagarmotha assists digestive function. Haldi provides antioxidant and anti-inflammatory properties, and Anar contributes astringent support for intestinal function. In the Ayurvedic management of IBD, Motion Stop Tablets can be considered supportive care for diarrhea and increased bowel frequency.
Dosage: 2 tablets twice a day after meals with plain water.
7. Vasaka Capsules
These contain Vasaka (Adhatoda vasica), can be included as supportive Ayurvedic therapy in the management of inflammatory bowel disease (IBD), particularly when Pitta-associated inflammatory features are prominent. Vasaka is recognized in Ayurveda for its Tikta and Kashaya Rasa and Pitta-pacifying properties. Its bioactive constituents, particularly vasicine and vasicinone, contribute to its pharmacological profile. The herb is also valued for antioxidant and anti-inflammatory activity, which may support tissue protection during persistent inflammatory states.
Dosage: 1 capsule twice a day after meals with plain water.
8. Coolstrin A Capsules
These contain Sheesham (Dalbergia sissoo), Vasaka (Adhatoda vasica), Anar (Punica granatum), Zandu (Jatropha curcas), and Arjuna (Terminalia arjuna). The combination can be considered as supportive Ayurvedic care for maintaining gastrointestinal health during chronic inflammatory bowel conditions. Sheesham and Vasaka provide traditionally recognized astringent and Pitta-supportive properties, while Anar helps support healthy bowel consistency. Arjuna contributes Kashaya properties along with antioxidant activity, and Zandu adds to the formulation’s herbal profile.
Dosage: 1 capsule twice a day after meals with plain water.
9. Coolstrin B Capsules
These contain Lodhra (Symplocos racemosa), Dhataki (Woodfordia fruticosa), Lajjalu (Mimosa pudica), Mochrus (Salmalia malabarica), and Nagkesar (Mesua ferrea). This combination provides herbs with predominantly Kashaya (astringent) and Grahi properties, making it relevant for supporting bowel regulation when loose stools and excessive intestinal secretions are present. Lodhra and Nagkesar are traditionally valued for supporting tissue integrity, while Lajjalu and Mochrus contribute astringent and restorative properties. Dhataki further supports gastrointestinal function and mucosal stability.
Dosage: 1 capsule twice a day after meals with plain water.
10. Aegle Plan Capsules
These contain Bilwa (Aegle marmelos), can be considered as supportive Ayurvedic care in inflammatory bowel disease (IBD), particularly when loose stools and disturbed bowel function are prominent. Bilwa is recognized for its Grahi, Kashaya, and Deepana properties, supporting stool consistency, digestive function, and intestinal stability. Its fruit contains bioactive constituents that contribute to its astringent and gastrointestinal-supportive profile.
Dosage: 1 capsule twice a day after meals with plain water.
11. Halorhena + Capsules
These contain Kutaja (Holarrhena antidysenterica), can be included as supportive Ayurvedic care in inflammatory bowel disease (IBD), particularly when frequent or loose stools are prominent. Kutaja is well recognized in Ayurveda for its Grahi, Kashaya, and Deepana properties, which support stool consistency, intestinal function, and digestive capacity. Its major alkaloids, including conessine, contribute to its pharmacological profile and gastrointestinal activity. In the Ayurvedic management of IBD, Halorhena + Capsules may help support bowel regulation and intestinal comfort during episodes of increased stool frequency.
Dosage: 1 capsule twice a day after meals with plain water.
12. Hemostop-B Powder
It is an Ayurvedic formulation containing Jhnadu, Priyangu (Callicarpa macrophylla), Parnabeej, Durva (Cynodon dactylon), Amalaki (Phyllanthus emblica), Lotus (Nelumbo nucifera), Punnag (Calophyllum inophyllum), Ayapan (Eupatorium ayapana), Raktniryas, and Mishri. The formulation brings together herbs traditionally valued for Kashaya (astringent), Raktasthambaka (blood-stabilizing), and Pitta-supportive properties. Amalaki and Durva provide antioxidant support, while Priyangu, Lotus, and Punnag contribute astringent properties that support tissue integrity.
Dosage: 1 teaspoonful twice a day after meals with plain water.
13. Mimosa-Di Capsules
These contain Lajwanti (Mimosa pudica), can be considered supportive Ayurvedic care in inflammatory bowel disease (IBD), particularly when frequent loose stools and intestinal irritation are present. Lajwanti is traditionally recognized for its Kashaya (astringent) and Grahi properties, which support healthy stool consistency and bowel regulation. Its plant constituents also contribute antioxidant and tissue-supportive activity, providing a rationale for its use in gastrointestinal disorders. In the Ayurvedic management of IBD, Mimosa-Di Capsules may help maintain intestinal stability and support digestive comfort during bowel disturbances.>
Dosage: 1 capsule twice a day after meals with plain water.
Conclusion
Upadoz / Upadacitinib represents an important development in the evolving management of inflammatory bowel disease by targeting JAK1-dependent intracellular signaling. Its ability to influence multiple cytokine pathways provides a distinct therapeutic approach for controlling intestinal inflammation in appropriately selected patients with moderate-to-severe ulcerative colitis and Crohn’s disease. Upadoz / Upadacitinib represents a modern targeted approach to inflammatory signaling, while Ayurveda provides a broader framework centered on digestive and systemic balance.